
Relieve Your Pain and Help Realign Your Bite Over Time
Morning temple headaches, ear fullness, neck tightness, or a jaw that clicks, locks, or aches when you chew — these are the everyday symptoms of TMD, a disorder of the temporomandibular joint, the chewing muscles, and how your bite comes together. If a generic night guard hasn't helped, the joint itself — not just your teeth — may be what needs attention.
Medically reviewed by Dr. Boris Zusin, DDS, FAGD, MBA, MS, Diplomate, American Board of Dental Sleep Medicine (ABDSM) · Last reviewed August 21, 2026
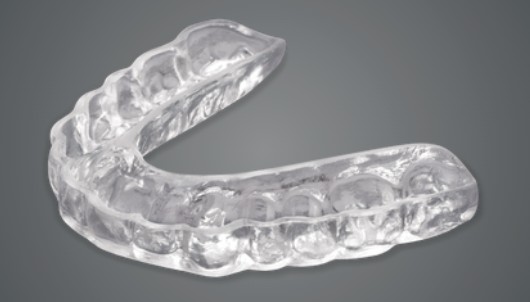
Relieve Stress and Alleviate Symptoms
A custom-made oral appliance adjusts your jaw into a proper position to relieve stress on the joint and ease TMD symptoms — typically worn only at night. Near Lincoln Center or elsewhere on the Upper West Side? See our TMJ Treatment Near the Upper West Side page for what the fitting and adjustment visits look like locally.
Am I a Candidate?
If you're experiencing jaw pain, clicking or popping, tension headaches, ear fullness, neck tightness, or facial muscle fatigue, an evaluation can determine whether a custom oral appliance is right for you.
If You've Already Tried a Night Guard and It Didn't Help
A lot of patients who come to us for TMJ care have already been fitted with a night guard somewhere else — and either chewed through it, woke up with their bite feeling different, or still have the same temple headaches every morning. That's usually a sign the appliance was solving the wrong problem. TMD rarely announces itself as just "joint pain" — it tends to show up as one of these:
Morning Temple Headaches
Dull, band-like pain across the temples is often muscle strain from the temporalis clenching all night against a bite that isn't stable — not a tension headache from stress alone.
Ear Fullness or Ringing, Without Infection
The jaw joint sits directly in front of the ear canal. Pressure or inflammation in the tissue behind the disc can irritate a nearby nerve and feel like ear fullness or tinnitus, even when an ENT finds nothing wrong with the ear itself.
Neck and Trapezius Tightness
Jaw strain and airway-related forward head posture often show up as compensatory tightness through the neck and upper trapezius — a pattern that's easy to mistake for a posture or gym injury.
Clicking, Locking, or a Jaw That Deviates
A jaw that clicks, catches, or shifts to one side as it opens usually points to the small disc inside the joint sitting out of its normal position — covered in detail below.
Not All Appliances Do the Same Job
This is usually why a prior night guard didn't help: most over-the-counter and even some custom guards are built to protect enamel, not to treat the joint.
| Device Type | What It Actually Does | Zusin Dental Perspective |
|---|---|---|
| Over-the-counter (boil-and-bite) | Soft, spongy plastic. Because it's something to bite into, it can stimulate the chewing reflex and, in some patients, make clenching and joint pain worse. | We generally advise against these for anyone with TMD symptoms. |
| Standard flat-plane night guard | A hard, flat acrylic surface that protects teeth from wear during grinding, but isn't designed or adjusted to change jaw position or take load off the joint. | Reasonable for simple wear protection; not enough on its own for active TMJ pain. |
| Custom therapeutic orthotic (deprogrammer) | Digitally mapped to your bite, designed to reduce pressure on the joint's retrodiscal tissue, balance the forces across your bite, and let the chewing muscles relax rather than stay braced all night. | Our standard clinical approach for patients with active TMD symptoms, not just tooth wear. |
If a previous night guard only protected your teeth and never touched your actual jaw pain, that's the difference — and it's worth an evaluation to see which category your symptoms fall into.
Is Your Nighttime Jaw Clenching Actually an Airway Problem?
Why treating TMJ pain sometimes requires looking beyond “stress” to how you breathe while you sleep.
Most patients with morning jaw soreness, a stiff neck, and chronic temple headaches are told the same thing: you're stressed, and you're grinding your teeth. The standard next step is usually a generic night guard — and while a flat guard can protect enamel from wear, plenty of patients find the jaw pain, muscle fatigue, and headaches stick around anyway. Nocturnal clenching and grinding don't always start with stress or the bite alone — for some patients, they're at least partly the jaw's response to a partially obstructed airway.
The Clenching Reflex: How the Airway Can Trigger Jaw Tension
During deep sleep, the muscles of the throat, tongue, and soft palate relax. In someone with a narrower airway or mild sleep-disordered breathing, that relaxed tissue can fall backward and partially obstruct airflow. When the brain registers that drop in airflow or rise in resistance, it triggers a brief micro-arousal — a protective reflex, not a conscious choice — and clenching or grinding often happens right at the tail end of it, as jaw and tongue muscles engage to help reopen the airway. Repeated many times a night, that repetitive muscle engagement is enough to leave the jaw joint and chewing muscles fatigued and sore by morning, even though no single episode involves sustained force.
Signs Your TMJ Symptoms May Be Linked to Sleep Breathing
- Jaw tension or temple headaches most mornings, even with a properly fitted flat night guard
- A partner has noticed loud snoring, gasping, or pauses in your breathing at night
- Unrefreshing sleep, midday fatigue, or brain fog despite a full night in bed
- Waking up with a dry mouth or sore throat
- Scalloped edges along the sides of your tongue (indentations from the tongue pressing against the teeth)
None of these on their own confirm sleep apnea — but together, they're a reasonable prompt to ask about your airway during a TMJ evaluation rather than treating the joint in isolation. That's part of why a thorough evaluation here includes asking about snoring, gasping, and daytime fatigue: treating clenching-driven TMD without ever asking about the airway risks missing the actual driver. If sleep apnea is confirmed alongside TMD, an airway-focused appliance is generally favored over a standalone flat splint, since a standard upper guard can, in some patients, reduce airway space rather than help it. See the fuller sleep apnea and grinding connection below, and our Sleep Apnea Treatment page for more.
A Two-Way Street, Not a One-Way Cause
The airway and the jaw joint are connected by shared anatomy — the position of the mandible, the hyoid bone, and the surrounding soft tissue affects both how you breathe and how your jaw joint is loaded. Research increasingly frames this as a genuinely bidirectional relationship rather than airway problems simply causing jaw problems: a compromised airway can drive TMJ pathology, and TMJ degeneration can in turn narrow the airway further, in a self-reinforcing cycle. A 2024 meta-analysis found that patients with TMD have roughly 2.5–2.7 times higher odds of having obstructive sleep apnea than people without TMD, with OSA present in an estimated 28.6% of TMD patients — a consistent finding across sleep-study-based and questionnaire-based diagnoses.
How the Airway Can Drive TMJ Pathology
Chronic mouth breathing — often from allergic rhinitis or enlarged tonsils/adenoids — tends to rotate the lower jaw backward and downward, loading the jaw joint in a way it isn't built for. Over time, that abnormal loading is associated with anterior disc displacement and osteoarthritic changes in the joint; in patients with obstructive sleep apnea specifically, more severe apnea tracks with a greater rate of disc displacement, seen in up to roughly 75% of severe OSA cases in one dataset.
How TMJ Pathology Can Narrow the Airway
The relationship also runs the other direction. Osteoarthritis in the jaw joint can shorten the condyle, which rotates the mandible, hyoid bone, and tongue base backward and downward — compressing the space behind the tongue and narrowing the airway. This matters most during adolescence, when it can restrict normal forward jaw growth, and a longitudinal study has linked progressive joint degeneration to a smaller airway and compensatory forward head posture.
A Distinct Pattern in Younger, Non-Obese Patients
A subset of TMD patients — typically younger, not obese, with a high arousal frequency during sleep but a fairly normal AHI — show a specific pattern on exam: forward head posture, loss of the normal neck curve, and a jaw joint sitting further back than usual. Researchers studying this group describe the backward-positioned joint as the body's adaptation to daytime breathing effort, not damage that needs correcting — an important distinction, since it argues against irreversible bite-changing procedures aimed at moving the jaw forward in this specific group. This is one more reason a thorough evaluation, not a one-size-fits-all appliance, matters.
Where Grinding Fits In
Sleep bruxism (teeth grinding) is common in both groups but especially frequent alongside OSA, likely because both are triggered by the same brief arousals and nervous-system activation during disrupted sleep — grinding episodes often follow a breathing event within seconds. That grinding, in turn, is one contributor to TMD and tooth wear, though the evidence for a direct causal chain is still considered low-quality rather than settled. Practically, this is one more reason airway-directed therapy can be relevant even when the presenting complaint is jaw pain: in patients using CPAP, treating the apnea has been shown to reduce bruxism-related episodes. One caveat worth noting: grinding alongside TMD doesn't by itself meaningfully raise a STOP-Bang score, so a low score in a patient who grinds shouldn't be read as reassurance if other OSA features (loud snoring, witnessed pauses, daytime fatigue) are present.
How We Actually Grade “Grinding” — It's Not All-or-Nothing
Sleep bruxism isn't a single yes/no finding — an international consensus framework grades it across three tiers of certainty, and knowing which tier applies changes how much weight to put on it. Possible sleep bruxism is based on self-report alone (you or a bed partner notice grinding sounds or a sore jaw on waking). Probable adds clinical exam findings — tooth wear facets, masseter or temporalis muscle tenderness on palpation, a scalloped tongue, or a ridged buccal mucosa (linea alba) — on top of the self-report. Definite sleep bruxism requires instrumental confirmation: a portable single-channel EMG/ECG recorder worn overnight, or polysomnography (PSG) with masseter EMG, which remains the gold standard but is expensive and not something most patients need just to start conservative treatment.
In everyday screening, the self-report tools that matter most are the STAB (Standardized Tool for the Assessment of Bruxism) Axis A questionnaire and the Oral Behaviors Checklist, both used to flag possible/probable sleep bruxism without requiring a sleep lab visit. A meta-analysis evaluating the accuracy of these tools against instrumental recordings found their agreement is only moderate at best — useful for flagging who's worth a closer look, not for confirming a diagnosis on their own.
An Important Caveat: Self-Report and Instrumental Studies Don't Always Agree
This is worth being direct about, since it changes how a positive screen should be interpreted. Studies that rely on questionnaires or self-reported grinding tend to find a positive association between sleep bruxism and TMD pain. Studies that instead use objective instrumental recordings (EMG, PSG) to confirm bruxism find that association is weaker, often not statistically significant, and in some analyses even runs in the opposite direction. In other words, the *belief* that you grind — or a partner's report that you do — correlates with pain more consistently than grinding actually measured overnight does. Practically, this means a positive questionnaire screen is a reasonable prompt to look closer at the jaw and muscles, but it shouldn't by itself be treated as proof that grinding is the driver of your pain, since the objective evidence for that causal link is considerably weaker than the self-report data alone would suggest.
Sleep bruxism prevalence itself is also notably higher in TMD populations than in the general population — studies of TMD patients find sleep bruxism in roughly 47–65% of cases, compared with about 8–13% in the general adult population. Separately, a retrospective cohort study found sleep bruxism to be an independent risk factor for TMD symptoms recurring after initial treatment, meaning it's not just a co-occurring nuisance but something that may specifically undermine how durable your improvement is if left unaddressed.
Practical takeaway: an appliance built to hold the jaw forward for TMJ relief may also change airway space, for better or worse depending on the design and your specific anatomy — which is part of why appliance selection here isn't generic, and why persistent TMD with any of the airway signs above is worth mentioning at your evaluation.
Should TMD Patients Be Screened for Sleep Apnea?
For patients with persistent TMD — especially alongside snoring, grinding, daytime fatigue, or a recessed jaw — the evidence supports case-finding rather than skipping the question. A 2024 meta-analysis explicitly recommended incorporating OSA screening into the routine TMD exam, and a 2026 study found TMD patients had nearly 8 times higher odds of screening high-risk for OSA than the general comparison group (24% vs. 4%). That said, this isn't a call to screen every dental patient regardless of symptoms: the U.S. Preventive Services Task Force found insufficient evidence to justify universal OSA screening in adults without symptoms, since no questionnaire has been well validated in an unselected population. The distinction that matters clinically is between case-finding in a higher-risk group — which persistent TMD reasonably qualifies as — and screening everyone, which isn't currently supported.
The STOP-Bang questionnaire is the most widely recommended first-line tool for this kind of case-finding: it's simple, well-validated, and highly sensitive (≥93%) for moderate-to-severe OSA, though it isn't very specific on its own, meaning plenty of positive scores won't turn out to be significant OSA. A score of 3 or higher is generally considered high risk and a reasonable trigger to discuss a referral for a sleep study — the only way to actually confirm a diagnosis. You can use the same screening tool we use with our sleep apnea patients right here:
STOP-Bang Sleep Apnea Risk Screening
STOP-Bang is a validated 8-item questionnaire used to estimate OSA risk. Answer all 8 questions, then click “See My Result.”
STOP-Bang is a validated OSA screening questionnaire, used here as a self-assessment tool — it is not a diagnosis. A score of 3 or higher has 88–94% sensitivity for moderate-to-severe OSA; a physician-ordered sleep study is the only way to confirm a diagnosis. Dentists can also weigh in with a Mallampati score and an oropharyngeal-narrowing check on imaging, both assessable during a routine exam.
Sources
- Association Between Obstructive Sleep Apnea and Temporomandibular Disorders: A Meta-Analysis — Machado CAO, de Resende CMBM, Stuginski-Barbosa J, et al., Journal of Oral Rehabilitation (2024)
- Association Between Mouth Breathing and the Temporomandibular System: A Narrative Review — Gu L, Gai K, Liu X, et al., Journal of Oral Rehabilitation (2025)
- Mouth Breathing Impairs the Development of Temporomandibular Joint at a Very Early Stage — Hu Z, Sun H, Wu Y, et al., Oral Diseases (2020)
- Associations Among Temporomandibular Joint Osteoarthritis, Airway Dimensions, and Head and Neck Posture — Kang JH, Journal of Oral and Maxillofacial Surgery (2020)
- Clinical Phenotype of South-East Asian Temporomandibular Disorder Patients With Upper Airway Resistance Syndrome — Tay DKL, Pang KP, Journal of Oral Rehabilitation (2018)
- Sleep-Related Breathing Disorders and Bruxism — Kostrzewa-Janicka J, Jurkowski P, Zycinska K, et al., Advances in Experimental Medicine and Biology (2015)
- Relationship Between Bruxism and Obstructive Sleep Apnea: A Systematic Review of the Literature — Doblado NG, Barrera Mora JM, Dorado FP, et al., Journal of Clinical Medicine (2025)
- Prevalence and Predictors of Sleep Bruxism in Patients With Obstructive Sleep Apnea and the Effect of Positive Airway Pressure Treatment — Dadphan N, Chalidapongse P, Muntham D, Chirakalwasan N, Sleep and Breathing (2024)
- Three-Dimensional Assessment of Pharyngeal Airway, Hyoid Bone, and Craniocervical Changes After Stabilization Splint Treatment in Temporomandibular Disorder Patients — Chen P, Al-Hadad SA, Rao C, et al., Scientific Reports (2025)
- Comparison Between Traditional and Digital Anterior Repositioning Splints on the Upper Airway in Skeletal Class II Malocclusion With TMJ Degenerative Disease — Luo S, Xu L, Deng Y, et al., Scientific Reports (2026)
- The Presence of Temporomandibular Disorder Is Associated With an Elevated Risk of Concomitant Sleep Apnea — Moradi A, Samieirad S, Shakiba R, et al., Journal of Oral and Maxillofacial Surgery (2026)
- Sleep Apnea Symptoms and Risk of Temporomandibular Disorder: OPPERA Cohort — Sanders AE, Essick GK, Fillingim R, et al., Journal of Dental Research (2013)
- Screening for Obstructive Sleep Apnea in Adults: US Preventive Services Task Force Recommendation Statement — US Preventive Services Task Force, Mangione CM, Barry MJ, et al., JAMA (2022)
- Evaluation and Management of Adults With Obstructive Sleep Apnea Syndrome — Lee JJ, Sundar KM, Lung (2021)
- Critical Issues in Dental and Medical Management of Obstructive Sleep Apnea — Lavigne GJ, Herrero Babiloni A, Beetz G, et al., Journal of Dental Research (2020)
- Diagnosis and Treatment of Obstructive Sleep Apnea — Lastra AC, Neborak JM, Mokhlesi B, JAMA Internal Medicine (2025)
- Application Value of Joint STOP-Bang Questionnaire and Epworth Sleepiness Scale in Screening for Obstructive Sleep Apnea — Zheng Z, Zhang Y, Chen M, et al., Frontiers in Public Health (2022)
- Prediction of Obstructive Sleep Apnea: Comparative Performance of Three Screening Instruments on the Apnea-Hypopnea Index and the Oxygen Desaturation Index — Veugen CCAFM, Teunissen EM, den Otter LAS, et al., Sleep and Breathing (2021)
- Utilization of the GOAL Questionnaire as a Standardized Screening Tool for Obstructive Sleep Apnea — Xing Y, Zhang Z, Yin J, et al., Scientific Reports (2023)
- Automatic Prediction of Obstructive Sleep Apnea in Patients With Temporomandibular Disorder Based on Multidata and Machine Learning — Lee YH, Jeon S, Auh QS, Chung EJ, Scientific Reports (2024)
- Clinical, Psychological, and Hematological Factors Predicting Sleep Bruxism in Patients With Temporomandibular Disorders — Lee YH, Chon S, Auh QS, et al., Scientific Reports (2025)
- Botulinum Toxins for Sleep Bruxism — Balanta-Melo J, Dallaserra M, Verdugo-Paiva F, et al., Cochrane Database of Systematic Reviews (2024)
- Validity of Different Tools to Assess Sleep Bruxism: A Meta-Analysis — Casett E, Réus JC, Stuginski-Barbosa J, et al., Journal of Oral Rehabilitation (2017)
- Validity of Patient Self-Reports and Clinical Signs in the Assessment of Sleep Bruxism Based on Home-Recorded Electromyographic/Electrocardiographic Data — Ohlmann B, Rathmann F, Bömicke W, et al., Journal of Oral Rehabilitation (2022)
- The Association of Self-Reported Awake Bruxism and Sleep Bruxism With Temporomandibular Pain and Dysfunction in Adult Patients With Temporomandibular Disorders — Chattrattrai T, Aarab G, Su N, et al., Clinical Oral Investigations (2023)
- Current Methods of Bruxism Diagnosis: A Short Communication — Pigozzi LB, Rehm DDS, Fagondes SC, et al., The International Journal of Prosthodontics (2019)
- Sleep Bruxism Is a Significant Risk Factor for the Recurrence of Temporomandibular Disorder: A Single-Center Retrospective Study — Yang Y, Qin JX, Yao Y, et al., Journal of Oral Rehabilitation (2025)
- Comparison of Ultrasonography-Based Masticatory Muscle Thickness Between Temporomandibular Disorders Bruxers and Temporomandibular Disorders Non-Bruxers — Lee YH, Chun YH, Bae H, et al., Scientific Reports (2024)
- Sleep Bruxism and Temporomandibular Disorders: A Scoping Review of the Literature — Manfredini D, Lobbezoo F, Journal of Dentistry (2021)
- Temporomandibular Disorders in Patients With Polysomnographic Diagnosis of Sleep Bruxism: A Case-Control Study — Sinclair A, Wieckiewicz M, Ettlin D, et al., Sleep and Breathing (2022)
- Temporomandibular Disorders: Priorities for Research and Care — National Academies of Sciences, Engineering, and Medicine, The National Academies Press (2020)
Comfortable Impressions, Even With a Limited Opening
Many TMD patients have a restricted jaw opening (trismus) by the time they seek treatment, which makes a heavy, gag-inducing impression tray genuinely difficult to tolerate. We capture the bite for your appliance with a digital optical scanner instead of traditional putty — no bulky tray held in place for minutes at a time, and no need to force an already-painful jaw open wider than it wants to go.
What the Research Says About TMD
TMD (temporomandibular disorder) is an umbrella term for musculoskeletal and neuromuscular conditions affecting the jaw joint, chewing muscles, and surrounding structures. It's genuinely common — an estimated 5–15% of adults have it, most often between ages 20 and 40, and it's roughly 1.5–2 times more common in women. Only about 5% of people with TMD actually need treatment, and for most patients, symptoms ease on their own over time regardless of what treatment, if any, is used.
How It's Diagnosed
Diagnosis is primarily based on a history and physical exam, with a detailed evaluation of the chewing muscles and jaw joint — not routine imaging. X-rays or advanced imaging are reserved for cases where a joint problem, degenerative disease, or bite issue is specifically suspected. The current validated diagnostic framework (called DC/TMD) looks at both the physical diagnosis — muscle pain, joint pain, disc displacement, or degenerative joint disease — and psychosocial factors like stress and coexisting chronic pain, since TMD is frequently accompanied by other chronic pain conditions and can be worsened by them.
How TMD Is Classified
“TMD” isn't one condition — it's an umbrella covering a range of distinct problems, and a 2020 National Academies of Sciences, Engineering, and Medicine report on TMD research and care lays out the full taxonomy. In practice, the common TMDs that dentists actually diagnose and treat — the ones with validated diagnostic criteria — fall into three categories: masticatory muscle disorders (muscle pain, most often myalgia or myofascial pain), temporomandibular joint disorders (joint pain, disc displacement, and degenerative joint disease like osteoarthritis), and headache attributed to TMD. Rarer conditions — jaw tumors, congenital or developmental jaw disorders, and fractures — also technically fall under the TMD umbrella, but currently only have clinical criteria rather than fully validated diagnostic criteria, since they're far less common and harder to study at scale.
Knowing which category your symptoms fall into matters clinically — a muscle-dominant presentation, a joint-dominant presentation, and a headache-dominant presentation aren't managed identically, even though they can overlap in the same patient. For a deeper look at how each pain type and joint finding is actually defined and told apart, see Myalgia, Myofascial Pain, Arthralgia, and Headache: The Different Kinds of TMD Pain.
What Happens During a TMJ Evaluation?
An evaluation starts with understanding your symptoms and how your jaw actually functions — not with automatically fitting a night guard. A typical visit includes:
- History: when your symptoms started, what makes them better or worse, any past TMJ treatment, and relevant dental or medical history.
- Jaw movement: how far you can open and how your jaw tracks as it opens and closes.
- Joint exam: checking the TM joints themselves for tenderness and joint sounds like clicking, popping, or crepitus.
- Muscle exam: palpating the chewing muscles for tenderness or overactivity.
- Bruxism check: looking for tooth wear, fractured teeth or restorations, and other signs consistent with grinding or clenching.
- Bite evaluation: how your upper and lower teeth meet.
- Deciding on next steps: imaging or a specialist referral isn't automatic — we order it only when the exam findings actually point that way.
That exam is what determines whether conservative self-care, an oral appliance, or referral makes sense for you, rather than starting from an appliance and working backward.
Why Does My Jaw Click or Lock?
The jaw joint has a small, cushion-like disc that sits between the jawbone (the condyle) and the socket in the skull, letting the joint glide smoothly as you open and close. Clicking and locking almost always trace back to this disc slipping out of its normal position — two different symptoms of the same underlying issue.
Why It Clicks
The most common cause is called disc displacement with reduction: with your mouth closed, the disc sits slightly forward of where it belongs. As you open, the jaw ball slides forward and snaps back underneath the disc — that snap is the click. This is genuinely common, accounts for a large share of TMD diagnoses, and is usually painless. On its own, without pain or limited movement, a click generally doesn't need to be “fixed” — reassurance and monitoring is the standard approach, not intervention, since exam reliability for joint sounds is limited and clicking by itself isn't a disease.
Why It Locks
Locking happens when the displaced disc actually blocks the jaw ball from sliding normally, rather than just getting snapped past:
- Intermittent locking — the disc mostly reduces as usual but occasionally catches, causing brief, self-resolving episodes where the jaw is momentarily hard to open fully.
- Closed lock (disc displacement without reduction) — the disc stops reducing altogether. This often follows a history of clicking that suddenly stops, replaced by sudden pain and a jaw that won't open more than about 20–25mm (roughly one and a half finger-widths, versus a normal 35–55mm), with the jaw deviating toward the affected side when trying to open.
- Open lock — a different problem entirely: the jaw gets stuck open rather than closed, from the joint slipping past its normal range. This needs prompt attention.
When to Get It Checked
Clicking alone, without pain or limited opening, is common and usually not something that needs treatment. It's worth an evaluation if clicking is joined by pain, if your jaw catches or locks even briefly, or if a click you've had for a while suddenly disappears and is replaced by a stiffer, harder-to-open jaw — that specific pattern can signal the disc has stopped reducing. Diagnosis is usually based on history and a physical exam; MRI is reserved for cases that aren't responding to conservative care or where the diagnosis genuinely isn't clear from the exam alone.
Conservative Treatment Comes First
Across published guidelines, there's real agreement that treatment should start conservative and reversible, then escalate only if needed. In order, that typically looks like:
- Education and self-management — reassurance that TMD is usually not progressive, a softer diet during flare-ups, avoiding clenching and wide yawning, heat or ice, and jaw relaxation techniques.
- Physical therapy — therapeutic jaw exercises combined with manual therapy have the best evidence support among physiotherapy approaches.
- Psychological therapy or CBT — addresses the stress and pain-coping side of TMD, particularly useful for chronic cases.
- Medication — NSAIDs and muscle relaxants first-line for pain flares; the evidence for long-term drug therapy in chronic TMD is generally low-quality.
- Oral appliances — still widely prescribed by dentists as a next step (see the honest caveat below).
- Escalation — arthrocentesis or arthroscopy for joint-based TMD that doesn't respond to conservative care, with open joint surgery reserved for severe, refractory cases.
Figure: the typical conservative-first treatment sequence for TMD — most patients improve in the first four steps.
An Honest Caveat About Oral Appliances
This is worth being direct about, since it's literally what we offer on this page. Occlusal splints remain widely used by dentists as an early treatment step, and one randomized trial found a stabilization splint measurably reduced TMD symptoms. But a 2022 rapid review of systematic reviews and guidelines took a more skeptical position, recommending against occlusal splint therapy for lack of strong supporting evidence — a genuine, unresolved disagreement in the literature rather than settled science either way. Separately, orthodontic treatment aimed at achieving an "ideal" bite has no solid scientific basis for preventing or treating TMD on its own.
What this means for you: a custom oral appliance is a conservative, reversible, low-risk option that many patients find genuinely helpful for symptom relief — but we don't present it as a proven cure backed by unanimous evidence, because that wouldn't be accurate. It typically makes the most sense alongside the self-management steps above, not as a replacement for them, and if your symptoms are severe, persistent, or not improving, that's a signal to talk about further evaluation rather than staying on an appliance indefinitely.
If You Also Grind Your Teeth: Why We Ask About Sleep Apnea
Teeth grinding and obstructive sleep apnea (OSA) overlap often — roughly 20–50% of adults with either condition show signs of the other. Current evidence doesn't establish that one directly causes the other in adults; the leading theory is that both are tied to the brief arousals that happen during disrupted sleep, with grinding tending to occur right at the tail end of one of these micro-wake-ups. Practically, that overlap matters for appliance selection: a standard upper occlusal splint can, in some patients, reduce space in the airway, which is the wrong direction if sleep apnea is part of the picture. If you also snore heavily, have been told you stop breathing or gasp during sleep, or feel excessively tired during the day, it's worth being screened for sleep apnea before we fit an appliance — when OSA is confirmed, an airway-focused option like a mandibular advancement appliance is generally preferred over a standalone upper splint, and treating the apnea often reduces the grinding as well. See our Sleep Apnea Treatment page for more.
“Do I Have TMJ Disorder?” Quiz
Answer all 7 questions, then click “See My Result” below.
This quiz is a screening tool, not a diagnosis. An exam is needed to confirm TMJ/TMD and rule out other causes.
Care From a Team That Knows You
Dr. Boris Zusin is an expert in general, cosmetic, implant, and dental sleep medicine, with 30+ years of clinical experience and ongoing continuing education. Lena Zusin, RDH works alongside him to make every visit as warm and comfortable as possible.
“Drawing upon our combined skills refined through years of experience and continued education, Lena and I will do everything possible to ensure that your entire dental experience at our office is as good as possible.” — Dr. Boris Zusin
- Uncompromising clinical excellence
- Meticulous attention to detail
- A gentle approach to dentistry

FAQ: TMJ Appliances at Zusin Dental, NYC
TMJ (temporomandibular joint) refers to the joint itself; TMD (temporomandibular joint disorder) refers to the condition affecting that joint. The terms are often used interchangeably, but TMD is technically the disorder.
- Jaw pain or soreness
- Tingling in the ear or neck
- Tension headaches
- Tenderness in the muscles on either side of your face
- Clicking or popping when opening/closing your jaw
- Tingling or numbness of the lips, chin, or cheek
- A change in your bite
- Facial muscle fatigue or earaches
A custom-made hard plastic appliance fits over your top or bottom teeth and gently repositions your jaw to relieve stress on the joint, easing TMD symptoms. It's typically worn only at night.
Dr. Boris Zusin performs a thorough exam of your jaw and face, may take X-rays to assess internal damage, then takes an impression so a dental lab can fabricate your custom appliance (usually about two weeks). Fit is checked and adjusted, and future visits may fine-tune it.
Sometimes, though it depends on how your specific plan classifies it. New York law doesn't allow health insurers to flatly exclude non-surgical TMJ treatment, but coverage still comes down to a case-by-case determination: if a plan treats TMD as a medical condition, medical benefits typically apply; if it's classified as dental, coverage depends on your dental plan's own exclusions. Custom oral appliances are sometimes covered in part by dental PPO plans. We're happy to help you check your specific benefits before starting treatment.
Look for a dentist with real experience diagnosing and treating TMD, not just fitting a generic night guard. Zusin Dental is located on the Upper West Side near Lincoln Center and sees patients from across Manhattan for jaw pain, clicking, and TMJ-related symptoms. Contact us to schedule an evaluation.
Jaw pain has several possible causes — TMD, dental problems like an abscess or cracked tooth, sinus issues, or referred pain from neck tension can all feel similar. TMD specifically tends to come with jaw clicking or popping, pain that's worse with chewing or wide yawning, or stiffness first thing in the morning. An exam is the only reliable way to sort out which is which, since self-diagnosis is often inaccurate.
Not quite. A generic, one-size-fits-most mouth guard mainly cushions your teeth. A custom TMJ appliance is fitted specifically to your bite and jaw position to actually reduce stress on the joint, which is why an off-the-shelf guard often doesn't do much for real TMD pain.
Yes — tension headaches, ear pain or a feeling of fullness in the ear, and even neck or shoulder tension are common TMD symptoms, since the jaw muscles and joint sit close to those structures. If headaches or ear pain come along with jaw clicking, tenderness, or a change in how your teeth fit together, TMD is worth ruling out.
Many patients notice some relief within the first few weeks, though how quickly symptoms improve varies with how long you've had TMD and how severe it is. We schedule follow-up visits to fine-tune the fit, since a well-adjusted appliance tends to work better than one that's left unchanged.
Not necessarily. Many patients wear their appliance only at night, and some are able to taper use over time as symptoms improve, especially if contributing factors like clenching or grinding are also addressed. Others with more chronic TMD find ongoing nightly use is what keeps symptoms controlled long-term — we reassess at follow-up visits rather than assuming one timeline fits everyone.
They can overlap, but they're not always the same thing. A standard night guard is primarily designed to protect your teeth from grinding (bruxism). A TMJ appliance is specifically designed and adjusted to reposition the jaw and reduce stress on the joint itself. Some appliances do both, but the design and adjustment approach differs depending on which problem we're targeting.
No — the two are designed for different jobs, even though both fit over your teeth and can look similar at a glance. A mandibular advancement device for obstructive sleep apnea is built primarily to hold the lower jaw forward during sleep to help keep the airway open. A TMJ appliance is designed around your jaw joints, chewing muscles, bite, and specific TMD findings, and its positioning goals aren't automatically the same as an airway-focused device. If you have both TMJ symptoms and diagnosed or suspected sleep apnea, that overlap needs to factor into which appliance — or combination — makes sense, which is part of why we ask about sleep symptoms during a TMJ evaluation. See our Sleep Apnea Treatment page for more.
General dentists routinely diagnose and treat straightforward TMD with conservative options like oral appliances, education, and lifestyle changes — which is where most cases start and where most resolve. More complex or persistent cases may be referred to an oral and maxillofacial surgeon or an orofacial pain specialist for advanced treatment. Dr. Boris Zusin evaluates your specific case and lets you know if a specialist referral makes sense. For a deeper look at how to weigh the two, see General Dentist or TMJ Specialist: Who Should Treat Your Jaw Pain?
No, and in most cases it shouldn't be the first option. Orthodontic treatment or bite adjustment (equilibration) aimed at achieving an “ideal” bite doesn't have solid scientific support for preventing or treating TMD on its own, and it's irreversible — you can't undo a reshaped bite the way you can stop wearing an appliance. Guidelines consistently favor starting with conservative, reversible options like education, physical therapy, and oral appliances, and reserving any bite-altering treatment for the rare case where it's genuinely indicated. If a bite correction is being proposed as a first step, it's worth getting a second opinion.
This is a conversation to have with both your sleep physician and your dentist rather than something to decide on your own, since it depends on how severe your apnea is and how well it's controlled. That said, alternating isn't unusual in practice: some patients use CPAP most nights and a mandibular advancement appliance while traveling or on nights CPAP isn't tolerated well. If you're using an oral appliance for OSA, it should be prescribed and fitted with your diagnosis in mind, not just adapted from a standard TMJ splint. Bring it up with your sleep physician before making the switch.
No — and this is a genuinely common experience. TMD pain doesn't always show up on standard exams because it's about how the jaw joint and chewing muscles are functioning, not something a sinus CT or neurological workup is designed to catch. Facial pain, ear fullness, and headaches that don't fit neatly into another specialty's diagnosis are exactly the kind of symptoms worth a dedicated TMD evaluation, which focuses specifically on jaw joint and muscle function that other specialists typically aren't examining for.
Teeth grinding in children is common and often outgrown, but loud or habitual snoring in a child is worth a pediatric evaluation regardless of TMJ — it's sometimes related to enlarged tonsils or adenoids and an airway issue rather than the jaw joint itself, and a pediatrician or pediatric ENT is usually the right first stop. If grinding is also causing visible tooth wear or your child complains of jaw or facial pain, we're happy to take a look, but treatment approaches in a growing child's jaw are different from adult TMD care.
Some patients with TMD report dizziness or balance-related symptoms, and the jaw joint does sit close to inner-ear structures, so a plausible anatomical link exists. That said, the evidence connecting TMD directly to vertigo is limited and mixed rather than well-established, and dizziness has many more common causes. If you're experiencing vertigo alongside jaw symptoms, it's worth ruling out inner-ear and neurological causes with the appropriate specialist rather than assuming TMD explains it.
Often, yes. Only about 5% of people with TMD actually need active treatment, and for most patients symptoms ease over time on their own regardless of what treatment, if any, is used. That's part of why conservative, reversible options come first — there's no need to jump to anything aggressive for a condition that tends to improve with time and self-management for most people. Persistent, worsening, or severe symptoms are the signal that it's worth a proper evaluation rather than waiting it out indefinitely.
It can mimic sinus symptoms, and occasionally the two occur together, which makes self-diagnosis unreliable. The jaw muscles and joint sit close to structures that drain and ventilate the sinuses, so referred pressure or discomfort in that region is plausible, though a direct causal link to nasal congestion specifically isn't well established. If you have facial pressure or congestion that isn't responding to typical sinus treatment, or that comes with jaw clicking, tenderness, or a change in your bite, it's worth having both possibilities evaluated.
Many patients report that their jaw pain feels worse in cold or rainy weather, similar to what people with arthritis often describe, but this hasn't been rigorously studied for TMD specifically and isn't something we'd present as an established fact. If you notice a pattern with weather, it's a reasonable thing to track and mention at a visit, but it shouldn't be relied on as a diagnostic clue on its own.
This is a legal and insurance question more than a medical one, so we can't give a definitive answer — it depends on the severity of your case and the specific policy, employer, or program involved. Severe, chronic TMD that significantly limits eating, speaking, or daily function can in some cases qualify for accommodations or disability benefits, but that determination is made by the relevant insurer or agency, not by a dental diagnosis alone. If this applies to you, your treating dentist can document your diagnosis and functional limitations to support whatever application process you're pursuing.
Anything that forces your jaw to work hard or open wide: whole apples and other foods that require a big bite, chewy foods like bagels, caramel, and gummy candy, hard foods like nuts and ice, and gum. A softer diet during flare-ups — things like eggs, pasta, fish, and cooked vegetables — reduces strain on the joint while symptoms settle down. This is meant as a temporary measure during flare-ups, not a permanent restriction.
Learn More From Our Blog
Sources
- Temporomandibular Disorders: Old Ideas and New Concepts — List T, Jensen RH, Cephalalgia (2017)
- Psychological Therapies for Temporomandibular Disorders (TMDs) — Penlington C, Bowes C, Taylor G, et al., Cochrane Database of Systematic Reviews (2022)
- Diagnosis and Treatment of Temporomandibular Disorders — Gauer RL, Semidey MJ, American Family Physician (2015)
- Efficacy of Stabilisation Splint Treatment on Temporomandibular Disorders — Niemelä K, Korpela M, Raustia A, Ylöstalo P, Sipilä K, Journal of Oral Rehabilitation (2012)
- Management of Temporomandibular Disorders: A Rapid Review of Systematic Reviews and Guidelines — Tran C, Ghahreman K, Huppa C, Gallagher JE, International Journal of Oral and Maxillofacial Surgery (2022)
- Temporomandibular Joint Dysfunctions: A Systematic Review of Treatment Approaches — González-Sánchez B, García Monterey P, Ramírez-Durán MDV, et al., Journal of Clinical Medicine (2023)
- Occlusal Interventions for Managing Temporomandibular Disorders — Singh BP, Singh N, Jayaraman S, et al., Cochrane Database of Systematic Reviews (2024)
- Temporomandibular Disorders: Rapid Evidence Review — Matheson EM, Fermo JD, Blackwelder RS, American Family Physician (2023)
- Temporomandibular Disorders — Burket's Oral Medicine, Wiley (2020)
- Pain, Function and Quality of Life in Temporomandibular Disorder Patients With Different Disc Positions — Journal of Oral Rehabilitation (2024)
- Sleep Bruxism and Obstructive Sleep Apnea: Association, Causality or Spurious Finding? A Scoping Review — Pauletto P, Polmann H, Conti Réus J, et al., Sleep (2022)
- Understanding the Clinical Management of Co-Occurring Sleep-Related Bruxism and Obstructive Sleep Apnea in Adults: A Narrative and Critical Review — Dal Fabbro C, Bornhardt-Suazo T, Landry Schönbeck A, de Meyer M, Lavigne GJ, Journal of Prosthodontics (2025)
- Sleep Bruxism in Respiratory Medicine Practice — Mayer P, Heinzer R, Lavigne G, Chest (2016)
- Association Between Obstructive Sleep Apnea and Temporomandibular Disorders: A Meta-Analysis — Machado CAO, de Resende CMBM, Stuginski-Barbosa J, et al., Journal of Oral Rehabilitation (2024)
- Association Between Mouth Breathing and the Temporomandibular System: A Narrative Review — Gu L, Gai K, Liu X, et al., Journal of Oral Rehabilitation (2025)
- Mouth Breathing Impairs the Development of Temporomandibular Joint at a Very Early Stage — Hu Z, Sun H, Wu Y, et al., Oral Diseases (2020)
- Associations Among Temporomandibular Joint Osteoarthritis, Airway Dimensions, and Head and Neck Posture — Kang JH, Journal of Oral and Maxillofacial Surgery (2020)
- Clinical Phenotype of South-East Asian Temporomandibular Disorder Patients With Upper Airway Resistance Syndrome — Tay DKL, Pang KP, Journal of Oral Rehabilitation (2018)
- Sleep-Related Breathing Disorders and Bruxism — Kostrzewa-Janicka J, Jurkowski P, Zycinska K, et al., Advances in Experimental Medicine and Biology (2015)
- Relationship Between Bruxism and Obstructive Sleep Apnea: A Systematic Review of the Literature — Doblado NG, Barrera Mora JM, Dorado FP, et al., Journal of Clinical Medicine (2025)
- Prevalence and Predictors of Sleep Bruxism in Patients With Obstructive Sleep Apnea and the Effect of Positive Airway Pressure Treatment — Dadphan N, Chalidapongse P, Muntham D, Chirakalwasan N, Sleep and Breathing (2024)
- Three-Dimensional Assessment of Pharyngeal Airway, Hyoid Bone, and Craniocervical Changes After Stabilization Splint Treatment in Temporomandibular Disorder Patients — Chen P, Al-Hadad SA, Rao C, et al., Scientific Reports (2025)
- Comparison Between Traditional and Digital Anterior Repositioning Splints on the Upper Airway in Skeletal Class II Malocclusion With TMJ Degenerative Disease — Luo S, Xu L, Deng Y, et al., Scientific Reports (2026)
- The Presence of Temporomandibular Disorder Is Associated With an Elevated Risk of Concomitant Sleep Apnea — Moradi A, Samieirad S, Shakiba R, et al., Journal of Oral and Maxillofacial Surgery (2026)
- Sleep Apnea Symptoms and Risk of Temporomandibular Disorder: OPPERA Cohort — Sanders AE, Essick GK, Fillingim R, et al., Journal of Dental Research (2013)
- Screening for Obstructive Sleep Apnea in Adults: US Preventive Services Task Force Recommendation Statement — US Preventive Services Task Force, Mangione CM, Barry MJ, et al., JAMA (2022)
- Evaluation and Management of Adults With Obstructive Sleep Apnea Syndrome — Lee JJ, Sundar KM, Lung (2021)
- Critical Issues in Dental and Medical Management of Obstructive Sleep Apnea — Lavigne GJ, Herrero Babiloni A, Beetz G, et al., Journal of Dental Research (2020)
- Diagnosis and Treatment of Obstructive Sleep Apnea — Lastra AC, Neborak JM, Mokhlesi B, JAMA Internal Medicine (2025)
- Application Value of Joint STOP-Bang Questionnaire and Epworth Sleepiness Scale in Screening for Obstructive Sleep Apnea — Zheng Z, Zhang Y, Chen M, et al., Frontiers in Public Health (2022)
- Prediction of Obstructive Sleep Apnea: Comparative Performance of Three Screening Instruments on the Apnea-Hypopnea Index and the Oxygen Desaturation Index — Veugen CCAFM, Teunissen EM, den Otter LAS, et al., Sleep and Breathing (2021)
- Utilization of the GOAL Questionnaire as a Standardized Screening Tool for Obstructive Sleep Apnea — Xing Y, Zhang Z, Yin J, et al., Scientific Reports (2023)
- Automatic Prediction of Obstructive Sleep Apnea in Patients With Temporomandibular Disorder Based on Multidata and Machine Learning — Lee YH, Jeon S, Auh QS, Chung EJ, Scientific Reports (2024)
- Clinical, Psychological, and Hematological Factors Predicting Sleep Bruxism in Patients With Temporomandibular Disorders — Lee YH, Chon S, Auh QS, et al., Scientific Reports (2025)
- Botulinum Toxins for Sleep Bruxism — Balanta-Melo J, Dallaserra M, Verdugo-Paiva F, et al., Cochrane Database of Systematic Reviews (2024)
- Validity of Different Tools to Assess Sleep Bruxism: A Meta-Analysis — Casett E, Réus JC, Stuginski-Barbosa J, et al., Journal of Oral Rehabilitation (2017)
- Validity of Patient Self-Reports and Clinical Signs in the Assessment of Sleep Bruxism Based on Home-Recorded Electromyographic/Electrocardiographic Data — Ohlmann B, Rathmann F, Bömicke W, et al., Journal of Oral Rehabilitation (2022)
- The Association of Self-Reported Awake Bruxism and Sleep Bruxism With Temporomandibular Pain and Dysfunction in Adult Patients With Temporomandibular Disorders — Chattrattrai T, Aarab G, Su N, et al., Clinical Oral Investigations (2023)
- Current Methods of Bruxism Diagnosis: A Short Communication — Pigozzi LB, Rehm DDS, Fagondes SC, et al., The International Journal of Prosthodontics (2019)
- Sleep Bruxism Is a Significant Risk Factor for the Recurrence of Temporomandibular Disorder: A Single-Center Retrospective Study — Yang Y, Qin JX, Yao Y, et al., Journal of Oral Rehabilitation (2025)
- Comparison of Ultrasonography-Based Masticatory Muscle Thickness Between Temporomandibular Disorders Bruxers and Temporomandibular Disorders Non-Bruxers — Lee YH, Chun YH, Bae H, et al., Scientific Reports (2024)
- Sleep Bruxism and Temporomandibular Disorders: A Scoping Review of the Literature — Manfredini D, Lobbezoo F, Journal of Dentistry (2021)
- Temporomandibular Disorders in Patients With Polysomnographic Diagnosis of Sleep Bruxism: A Case-Control Study — Sinclair A, Wieckiewicz M, Ettlin D, et al., Sleep and Breathing (2022)
- Temporomandibular Disorders: Priorities for Research and Care — National Academies of Sciences, Engineering, and Medicine, The National Academies Press (2020)
Your Experience Matters To Us
5.0 out of 5 on Google (54 reviews) · 4.99 out of 5 on Zocdoc (227 reviews)
“Knowledge is an understatement when you talk about Dr. Zusin! My family and I have been patients of his for over 20 years. I always feel I am given the best advice and never pressured into any unnecessary treatment.”
Faina S. · View on Google →
“I tried a couple different dentists in NYC and Zusin Dental is the best. They are thorough, they don't try and upsell you services you don't need, and they offer appointments on Saturday. The best cleaning I ever had!”
Gordon T. · View on Google →
“Routinely SUPERB level of care, including Dr. Zusin having made himself available for emergent care when needed. The office is always spotlessly clean and there is no waiting at appointment time. Pain-free dentistry!”
Anil N. · View on Google →
“I have never experienced pain with Dr. Zusin. For a practice in busy Manhattan, their office has a small town feel, very relaxed and personable. Lena is always quick to respond to appointment requests or changes.”
Molly P. · View on Google →
“Dr. Zusin is the best dentist! I have been visiting his office for the majority of my life. He has expertly performed teeth whitening and Invisalign, and continued to save my teeth after I chipped my two front teeth.”
Sasha S. · View on Google →
“The West End office is state of the art and very relaxing. Dr. Zusin and Lena are a great team. No matter the dental problem you will get the best results. I highly recommend them.”
Domingo Q. · View on Google →
Ready to Get Started?
You will never be treated like a statistic at Zusin Dental. Let's talk about what's right for you.
Schedule Your Visit Call 212-877-7475