
How to Handle a Chipped or Cracked Tooth Right Now
What you do in the first few minutes after chipping or cracking a tooth can affect how it's treated — here's a clear first-aid checklist...
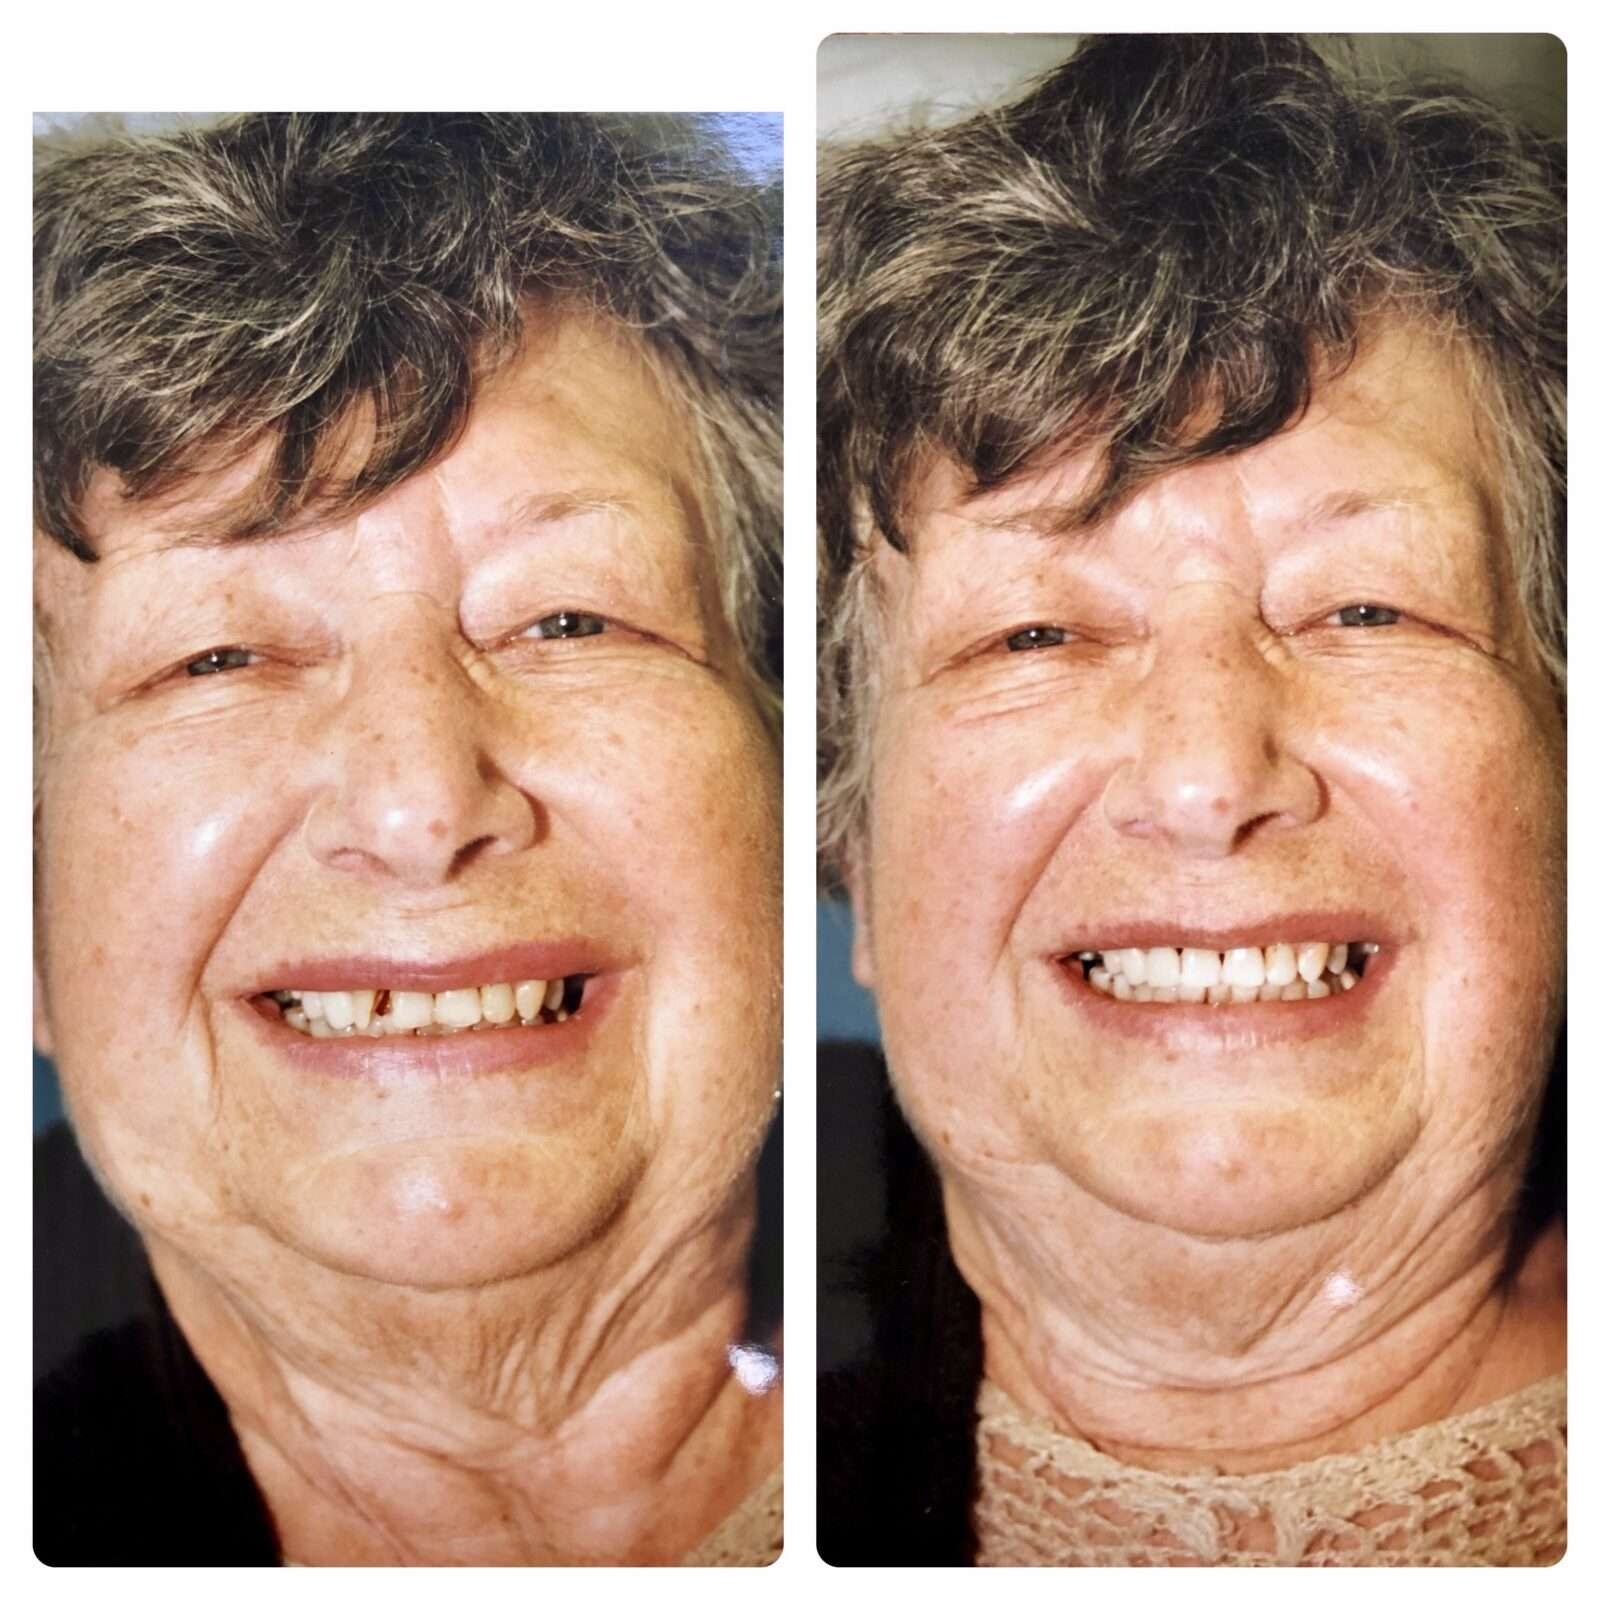
By Dr. Boris Zusin · Published August 8, 2026
A chipped or cracked tooth almost always happens at the worst possible moment. What you do in the first few minutes matters, so here's a clear, practical checklist.
Right Away
Rinse your mouth gently with warm water to clear any debris. If you can find the broken piece, save it in a small container with a little milk or water and bring it with you — it's occasionally usable in the repair. A cold compress against the cheek near the area helps with both pain and swelling, and avoid chewing on that side until you're seen.
How Urgent Is It?
A small chip with no pain can usually wait for a next-day appointment. Significant pain, a crack extending toward the gumline, a sharp edge cutting your tongue or cheek, or sensitivity to hot and cold are all reasons to call us the same day — the deeper a crack goes, the more time-sensitive it becomes.
What Treatment Usually Looks Like
Small chips are often fixed the same day with composite bonding. Larger fractures, or ones that compromise more of the tooth's structure, typically need a crown to fully protect and restore it. If a crack has reached the tooth's nerve, a root canal referral may come into the picture before restoration.
Are Those Fine Lines in My Teeth Cracks? (Craze Lines)
Many adults notice thin vertical lines on their front teeth, especially in bright light. These are usually craze lines: superficial, incomplete cracks that stay within the outer enamel layer. They do not reach the dentin or the nerve, they typically cause no pain or sensitivity, and apart from appearance they usually have no clinical significance. They become more common with age; in one imaging study, about half of upper central incisors had them, more often in adults than in teenagers and more severe after age 40. Braces and the removal of bonded brackets did not make them more likely.
Everyday chewing forces and temperature swings cause fine cracking in enamel, and the enamel’s structure normally stops those cracks from spreading, so with healthy saliva they rarely decay. Conditions that dry or weaken enamel, such as head and neck radiation or methamphetamine use, make them more frequent. Craze lines need no treatment; if they bother you cosmetically, tell us and we can discuss options. What we do watch for is a line that is actually deeper. It is not always possible to confirm by eye that a crack stops at the enamel, so we check them at your regular visits. New pain on biting, a pain that is sharpest when you release, new cold sensitivity, or staining along the line suggests a true cracked tooth, which is a different problem: we test with a bite stick and a light, and a crack that reaches dentin usually needs a restoration covering the cusps.
When the Break Is Below the Gumline: Pulling the Tooth Up
If a tooth is broken or decayed down to or below the gum, there may not be enough healthy tooth above the gum to hold a crown. One way to save it is orthodontic extrusion: a small bracket and wire gently pull the root upward so more sound tooth shows above the gum. The speed of the pull is chosen on purpose, depending on the goal. A rapid pull, usually a few weeks, uses heavier force and a brief gum-fiber release each week so the gum and bone stay where they are and the broken edge is exposed; in one published protocol the tooth moved about 2 mm while the gum moved only about 1 mm and the bone about a third of a millimeter. A slow pull uses very light force over months so the gum and bone travel up with the tooth, which is used when we want to build up the tissue, for example before an implant. After the move, the tooth is held steady, usually for about six weeks after a rapid pull and longer after a slow one, so it does not drift back.
Done carefully this is gentle on the gums, and root damage is uncommon, though heavy, prolonged force raises the risk, so we watch it with X-rays. It is not suitable for every tooth: a tooth with a fractured root, a very short root, a tooth fused to the bone, or one whose roots would be exposed at the fork cannot be pulled up safely, and the alternatives are minor gum surgery or replacing the tooth.
For a front tooth broken below the gum, the sequence is: root canal treatment first if the nerve is damaged, because the treated canal and a post or bonded attachment give the pull something to hold; then about a month of weekly visits during a rapid pull, with a quick gum-fiber release at the first and second visits and a bite check each time so nothing blocks the movement; then at least several weeks of holding the tooth steady before the final crown. The aim is typically 2 to 3.5 millimeters of movement, enough to leave about 2 millimeters of healthy tooth above the gum for the crown to grip. In published studies about 94 percent of extensively damaged teeth treated this way were still in function after an average of three years; the most common problem is the tooth drifting partway back during holding, which is why that stage is not rushed and sometimes needs a repeat pull before the crown. Root shortening from the pull was not found to be a clinically meaningful problem in the research reviews.
Pulling the tooth up versus trimming the gum and bone. The other common way to expose a broken edge is crown lengthening, a minor surgery that removes gum and bone. For a front tooth the pull usually comes out ahead: lengthening shortens the root’s bony support while making the visible tooth longer, so the tooth ends up with a less favorable crown-to-root balance, and it can leave the neighboring teeth with less bone, receding gums and black triangles. In laboratory tests, extrusion left the crown-to-root ratio roughly 22 to 30 percent better than lengthening. The trade-off is time: extrusion takes more visits and weeks to months, costs more, and needs a holding period, while lengthening is a single quicker procedure. No study has yet followed the two methods head-to-head over many years, so this recommendation rests on mechanics and smaller studies, and we will tell you which we favor for your tooth and why.
How we decide whether a tooth is worth saving. One measure dentists use is the crown-to-root ratio: how much of the tooth is above the bone compared with the root held in it. A ratio of about 1 to 1.5 is considered ideal and 1 to 1 the minimum, but those numbers are rules of thumb from expert opinion, not proven cutoffs. In one ten-year study of root-canal-treated back teeth that had crown lengthening, teeth that ended up at 1 to 1 or worse had the lowest survival, about 40 percent. That is why we try not to push a tooth past that line, and why pulling a tooth up, which changes the ratio less than trimming bone, can be the better choice. The ratio is only one factor, though. How much healthy tooth remains above the gum, a collar of tooth for the crown to grip, the health of the root canal, and the gum and bone around the tooth usually count for more. X-rays can also under- or over-state the ratio, so we judge the whole tooth rather than one number.
The order we weigh things in. First, how much of the tooth is left above the gum: a tooth with all four walls remaining, or at least about 3 mm of height, does best. Second, whether a collar of sound tooth, roughly 1.5 to 2 mm tall, can wrap the crown; research pooling many studies found this collar makes the tooth meaningfully harder to fracture and improves survival, and even a partial collar on two or more sides still helps. A post helps mainly when little tooth is left, and it does not replace a collar. If a collar can be created by pulling the tooth up, we plan that before the crown. Only then do we look at the crown-to-root ratio, which becomes the deciding factor mainly at its extremes. If no collar can be achieved by any method, we talk honestly about replacing the tooth.
What About a Crack Under an Existing Crown?
A crown protects a tooth, but it doesn't make the tooth underneath indestructible — the natural tooth structure beneath a crown can still crack, usually at the root or right at the margin where the crown meets the gumline. The tricky part is that you can't see it happening, so it usually shows up as symptoms rather than a visible chip: pain when you bite down or release a bite (a classic sign, since the crack flexes open and shut), sharp pain when the tooth is exposed to hot, cold, or sweets, intermittent pain that's hard to pin to one exact spot, or the crown itself starting to feel loose or shift slightly. A dull, lingering ache after chewing on that side is also worth paying attention to.
If you notice any of these signs in a crowned tooth, don't wait for it to become an emergency — a crack under a crown can worsen and reach the nerve if left untreated. We'll need to remove or X-ray through the crown to actually see what's happening underneath, so this isn't something to try to diagnose yourself at home.
Dealing with this right now? Don't wait — call our office for same-day emergency care.
Sources
- Cracked Tooth — Boushell LW, Journal of Esthetic and Restorative Dentistry (2009)
- Ferrule Dimensions and Restoration Outcomes in Endodontically Treated Teeth: A Systematic Review and Meta-Analysis — Hajeer O, Hasan A, Kanout C, Morad ML, Journal of Prosthodontics (2026)
- Prognostic factors in the decision to retain or extract a tooth — Orishko A, et al., Periodontology 2000 (2024)
- The Effect of Crown Lengthening on the Outcome of Endodontically Treated Posterior Teeth: 10-Year Survival Analysis — Patil K, Khalighinejad N, El-Refai N, Williams K, Mickel A, Journal of Endodontics (2019)
- Inconsistency in the Crown-to-Root Ratios of Single-Rooted Premolars Measured by 2D and 3D Examinations — Hong HH, Liu HL, Hong A, Chao P, Scientific Reports (2017)
- Orthodontic Forced Eruption of Permanent Anterior Teeth With Subgingival Fractures: A Systematic Review — Reichardt E, Krug R, Bornstein MM, et al., International Journal of Environmental Research and Public Health (2021)
- Forced Orthodontic Extrusion to Restore Extensively Damaged Anterior and Premolar Teeth as Abutments for Single-Crown Restorations: Up to 5-Year Results From a Pilot Clinical Study — Bruhnke M, Beuer F, Böse MWH, Naumann M, Journal of Prosthetic Dentistry (2023)
- A Systematic and Comprehensive Protocol for Rapid Orthodontic Extrusion — Crljenica MU, Perasso R, Imelio M, Viganoni C, Pozzan L, Journal of Esthetic and Restorative Dentistry (2024)
- Periodontal Considerations During Orthodontic Intrusion and Extrusion in Healthy and Reduced Periodontium — Antonarakis GS, Zekeridou A, Kiliaridis S, Giannopoulou C, Periodontology 2000 (2024)
- The orthodontic-periodontic interrelationship in integrated treatment challenges: a systematic review — Gkantidis N, Christou P, Topouzelis N, Journal of Oral Rehabilitation (2010)
- Extrusion Techniques - Clinical Applications of Modern Tooth Preservation Concepts and Their Comparison — Völler E, Stimmelmayr M, Güth JF, et al., Journal of Esthetic and Restorative Dentistry (2026)
- Cracked Teeth: A Review of the Literature — Lubisich EB, Hilton TJ, Ferracane J, Northwest Precedent, Journal of Esthetic and Restorative Dentistry (2010)
- The Influence of Age and Orthodontic Debonding on the Prevalence and Severity of Enamel Craze Lines — Oh C, Lee H, Kim J, et al., Journal of the American Dental Association (2023)
- Review of Cracked Tooth Syndrome: Etiology, Diagnosis, Management, and Prevention — Li F, Diao Y, Wang J, et al., Pain Research & Management (2021)
- Pathophysiology of Demineralization, Part I: Attrition, Erosion, Abfraction, and Noncarious Cervical Lesions — Roberts WE, Mangum JE, Schneider PM, Current Osteoporosis Reports (2022)
Related to This Article
Have a Dental Question of Your Own?
Reach out and we'll help you find the right next step.
Schedule Your Visit Call 212-877-7475