
Ready to Get a Straighter Smile Without Traditional Braces?
You may be a candidate for Invisalign® if you have crooked or crowded teeth, or a gap between your front teeth. Aligners only work on teeth that are healthy and free of decay.
Medically reviewed by Dr. Boris Zusin, DDS, FAGD, MBA, MS, Diplomate, American Board of Dental Sleep Medicine (ABDSM) · Last reviewed August 21, 2026
Say Goodbye to Metal Wires and Brackets
Invisalign® works by applying gentle, continuous pressure that shifts your teeth over time. You'll receive a new set of clear aligners about once a week, each one gradually adjusting your teeth toward their final position. Near Lincoln Center or elsewhere on the Upper West Side? See our Invisalign Near the Upper West Side page for what regular check-ins look like locally.
Dr. Boris Zusin is a recognized Invisalign® Preferred Provider, offering Invisalign since 2000 and completing hundreds of cases along the way — part of 30+ years practicing dentistry since 1995.
Am I a Candidate?
Invisalign® is an option for most adults and teens with mild-to-moderate crowding, spacing, or bite issues. A consultation with digital scans and 3D imaging will confirm whether it's the right fit for your smile.
What Invisalign® Can Actually Treat
Invisalign works well for a range of bite problems — not just minor gaps. Here's what it handles well, case type by case type, and where its real limits are.
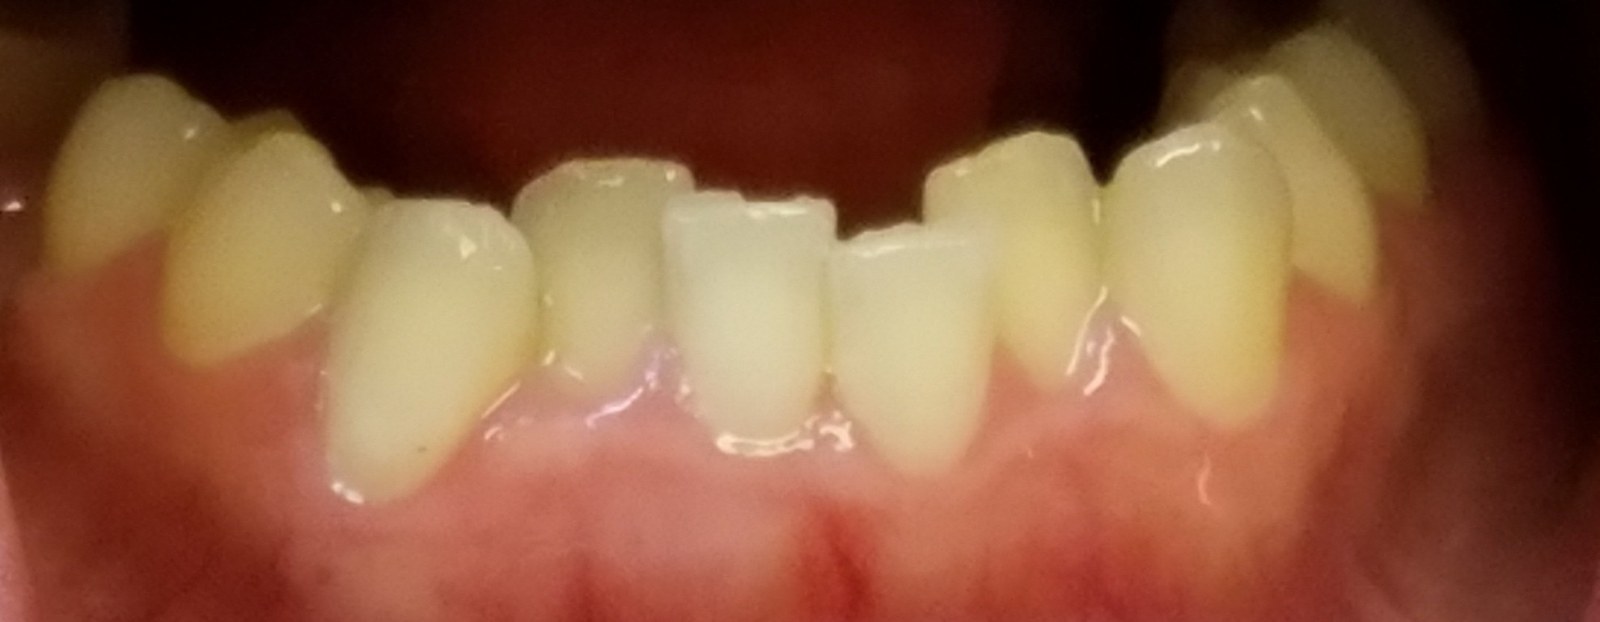
Crowding & Spacing
Crowding (teeth overlapping or rotated from lack of room) and spacing (gaps between teeth) are Invisalign's strongest use case. Mild-to-moderate crowding and spacing are considered ideal, non-extraction indications, where aligner results are most comparable to braces.
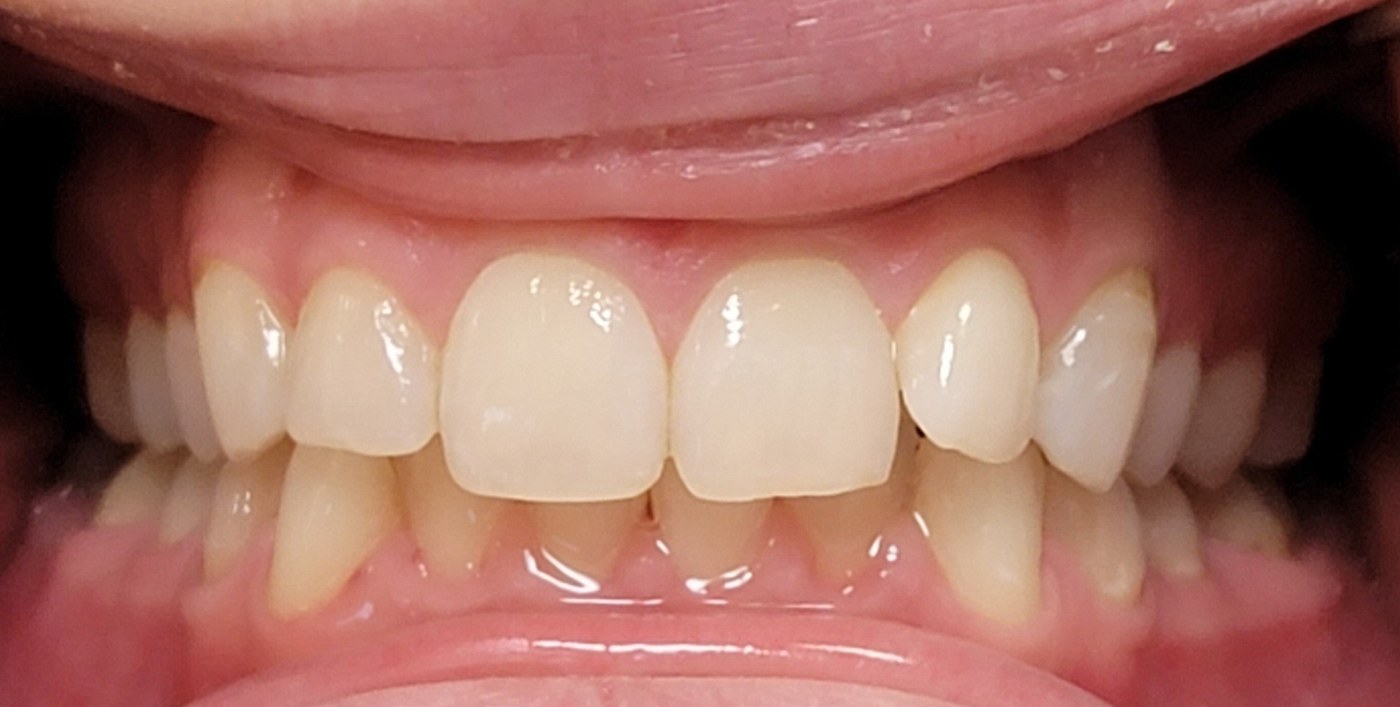
Overbite (Deep Bite)
Where the upper front teeth cover too much of the lower front teeth, targeted attachments and bite ramps can intrude and reposition the front teeth. Left unaddressed for years, a severe deep bite can wear the lower teeth down significantly — see a real example in our FAQ below. Mild-to-moderate cases tend to respond reliably; severe or skeletal deep bites may need a combined or referred approach.
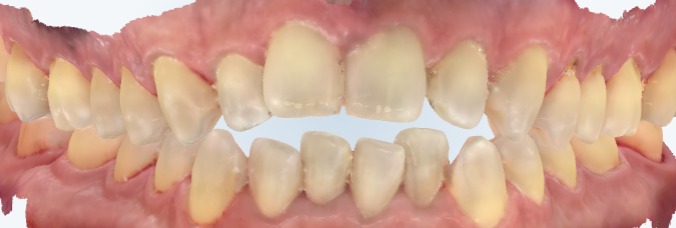
Open Bite
Where the front teeth don't touch when the back teeth are closed, aligners can extrude and reposition the front teeth to close the gap. This is one of the more studied uses of Invisalign — recent research puts closure success roughly in the 55–70% range, meaning most patients see real improvement, but a second round of aligners (a "refinement") to finish the correction is common and something we plan for from the start.
Crossbite & Narrow Arch
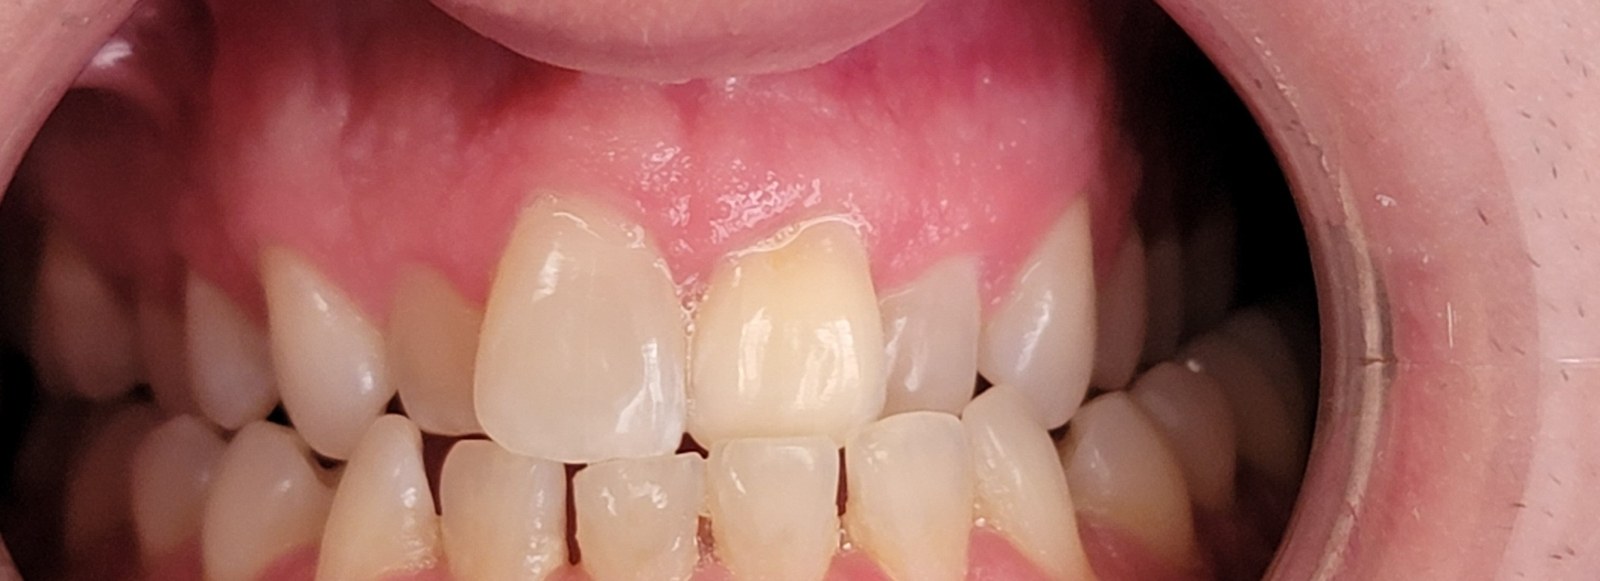
Aligners can gently widen a narrow upper arch and correct a crossbite (where upper teeth sit behind their lower counterparts) through controlled expansion. This tends to be most predictable in the lower arch and canine region; larger planned expansions and existing posterior crossbites are harder to predict precisely, which is why we track progress with scans along the way rather than assuming the initial plan will play out exactly as designed.
Where Invisalign has real limits: a true skeletal Class II ("overbite" from a small lower jaw) or Class III ("underbite") jaw relationship, very severe crowding, or corrections requiring precise rotation, torque, or extrusion of individual teeth are movements aligners handle less predictably than braces. More complex cases may need braces, a combined approach, or a referral to an orthodontist — we'll tell you plainly which category your bite falls into at your consultation. For the full breakdown of bite types and jaw relationships, see our Understanding Your Bite guide.
Invisalign® vs. Traditional Braces
Both work by applying continuous, gentle pressure to move teeth. The real differences are in day-to-day experience and where each has the clinical edge.
| Invisalign® / Clear Aligners | Traditional Metal Braces | |
|---|---|---|
| Appearance | Clear, barely noticeable | Visible metal (ceramic/clear brackets available at added cost) |
| Removable? | Yes — take out to eat, brush, and floss | No — fixed in place for the full treatment |
| Oral hygiene | Easier — brush and floss normally | Harder — extra care needed around wires and brackets |
| Diet restrictions | None — aligners come out to eat | Avoid sticky, hard, and crunchy foods |
| Comfort | Smooth plastic, less soft-tissue irritation | Wires and brackets can rub the cheeks and lips |
| Compliance required | High — needs 20–22 hours/day of wear to work | Low — works regardless of patient effort |
| Best suited for | Mild-to-moderate crowding, spacing, and bite issues | Mild through complex/severe cases, including larger jaw discrepancies |
| Precise movements (rotation, torque, extrusion) | Less predictable — achieved movement often falls short of the digital plan | More predictable — direct mechanical control over each tooth |
| Root resorption | Generally lower or comparable in current studies | Generally low, though slightly higher in some studies |
| Office visits | Fewer, shorter check-ins | More frequent adjustment visits |
| Mid-treatment plan changes | Refinement aligners (often 2–3 additional scans) are a normal part of many cases | Wire and bracket adjustments as needed |
| After treatment | Lifelong retainer wear needed, same as braces | Lifelong retainer wear needed |
| Typical cost in NYC | About $3,500–$8,000 | About $3,000–$7,000, up to $10,000 for complex cases |
The honest short version: for mild-to-moderate, non-extraction cases — the most common reason patients consider Invisalign — clinical outcomes between aligners and braces are broadly similar, and aligners tend to mean fewer visits and easier hygiene along the way. For more complex cases, extractions, or corrections needing significant rotation or tooth extrusion, braces still have the edge in achieving a precise final result. Both require a retainer indefinitely afterward — no orthodontic result, aligners or braces, is permanently stable without one. We'll tell you plainly at your consultation which category your case falls into, rather than assuming aligners are automatically the right fit.
Real Cases: Resolving Crowding and Improving Arch Form
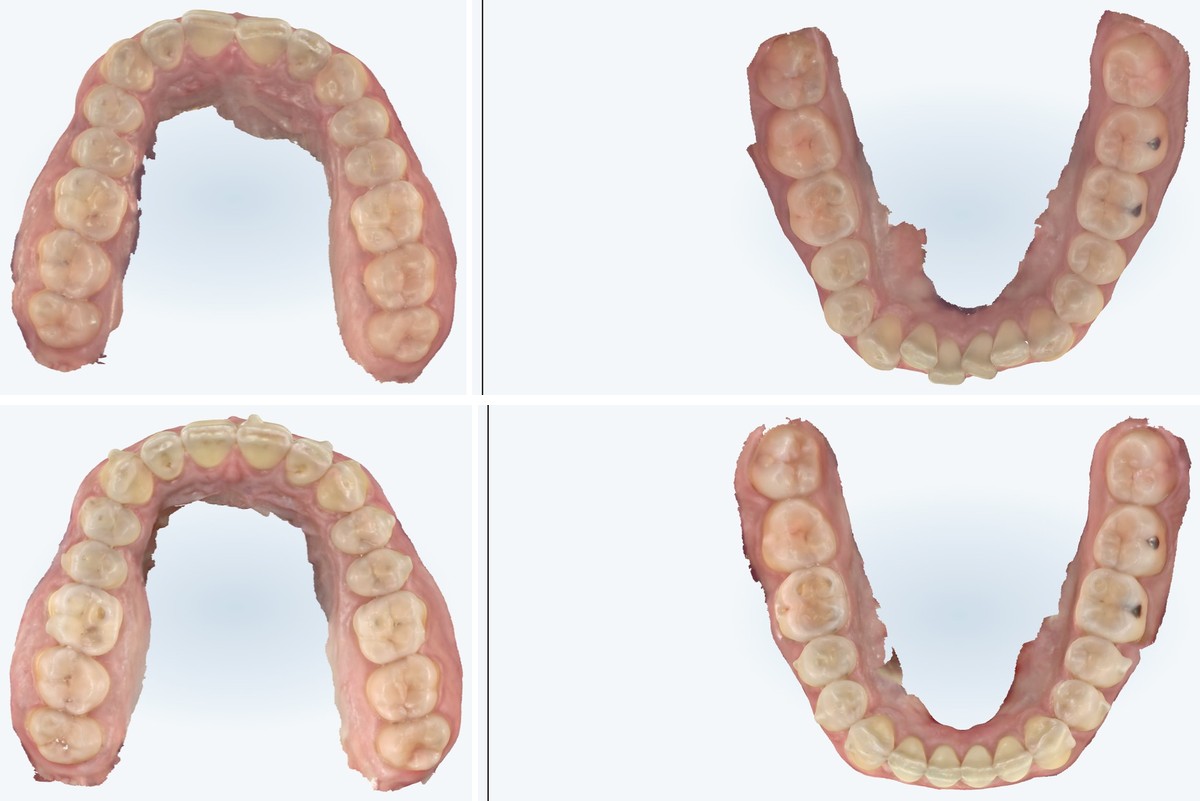
Case 1
These are real digital scans of a Zusin Dental patient's lower arch — before treatment (top row) and after (bottom row), each shown from two angles. The crowded, overlapping front teeth were unwound into a smoother, more evenly rounded arch, with proper room restored for each tooth.
Attachments: Small tooth-colored composite shapes were bonded to specific teeth to give the aligners more grip and leverage on the harder movements — mainly rotating and upright teeth that had tipped or twisted out of the arch from crowding. Without an attachment, an aligner can slide over a tooth's smooth surface without ever fully executing that motion.
Interproximal reduction (IPR): In a few spots, a very small amount of enamel — a fraction of a millimeter, well within the safe range for healthy enamel — was carefully removed between the contact points of neighboring teeth. This is a routine, incremental part of many crowding cases: it creates just enough space to unwind the crowding without needing to remove a tooth, and it's typically done at specific stages along the way, not all at once.
Retainers afterward: Once the arch reached this final form, a Vivera® retainer became part of holding it there. Teeth continue to have a natural tendency to drift for life, so the retention plan doesn't end when the last aligner tray does — see below for how we approach retainers long-term.
Case 2
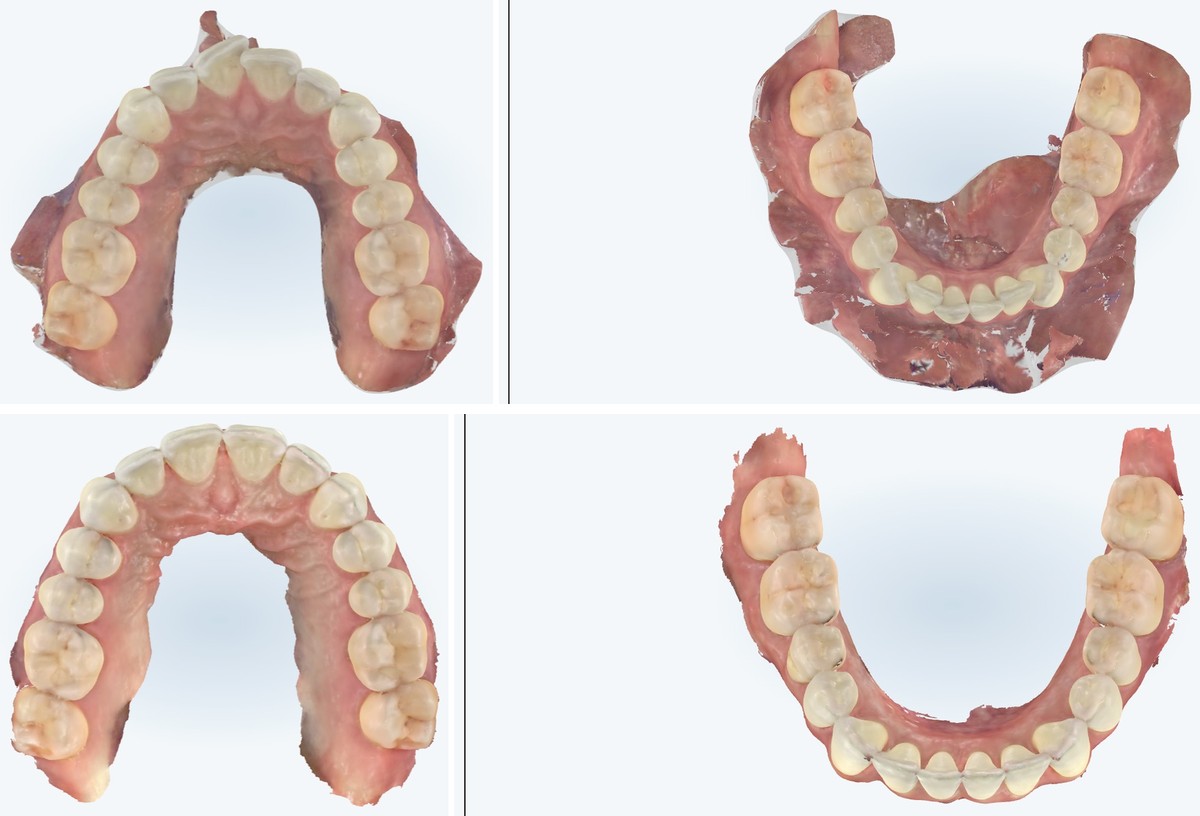
A second real crowding case — before treatment (top row) and after (bottom row), each shown from two angles. Here too, aligners gradually guided the crowded front teeth back into a more even, properly spaced arch.
As with the first case, this treatment plan relied on the same core tools: targeted attachments where extra grip was needed for rotation, small, staged amounts of interproximal reduction to create room without extractions, and a retainer once the final position was reached to hold the result in place long-term.
Every crowding case is different — the exact mix of attachments, IPR, and treatment length depends on how much rotation and overlap is present at the start. We'll map out the specific plan for your bite at a consultation with digital scans.
Case 3
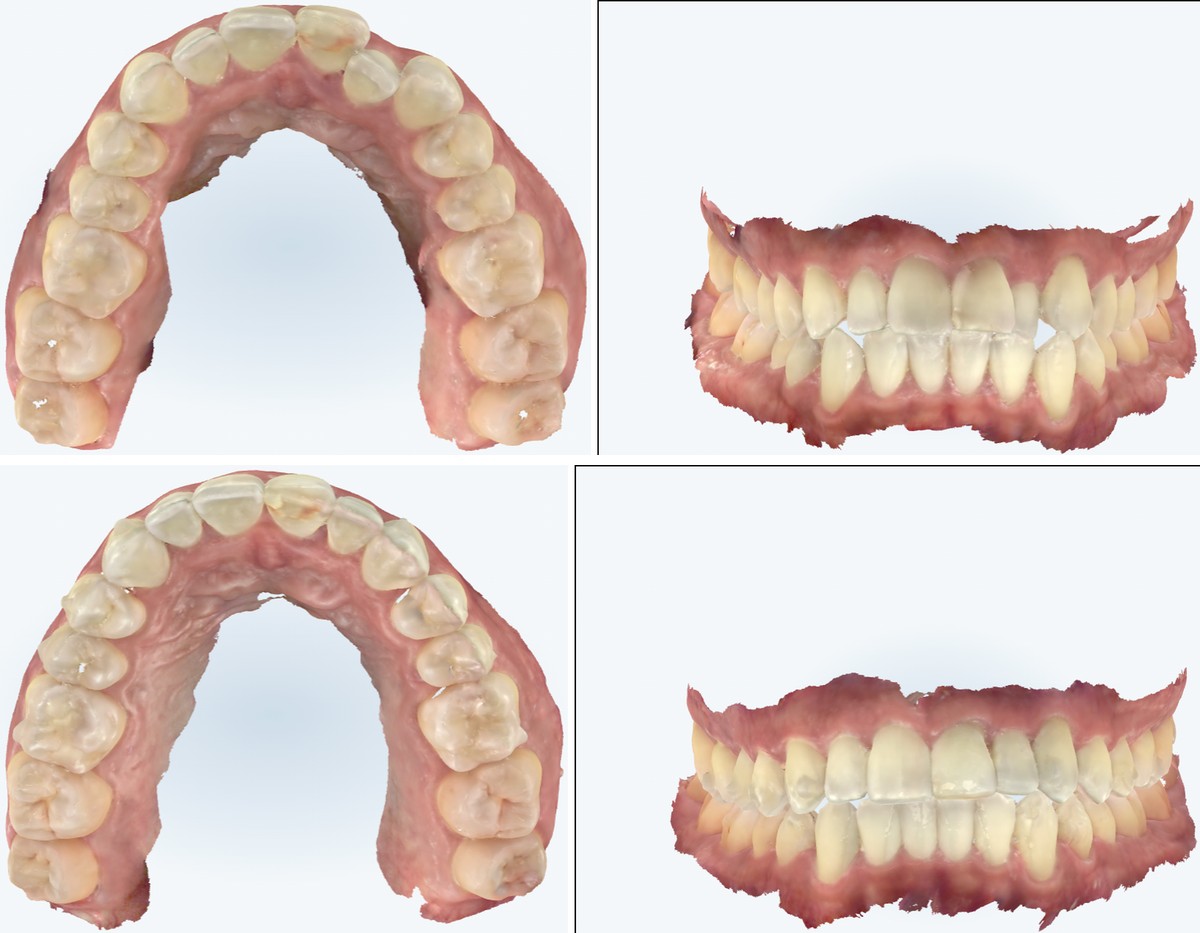
A third real case, combining crowding with an anterior crossbite — before treatment (top row) and after (bottom row), each shown from two angles. An anterior crossbite is when one or more upper front teeth sit behind their lower counterparts instead of in front of them, the reverse of a normal bite relationship.
Correcting a crossbite alongside crowding takes more coordinated tooth movement than crowding alone: the aligners not only unwind the overlapping teeth but also reposition specific teeth forward or backward to re-establish a normal front-tooth relationship. This case used the same core tools as the others — attachments for the harder rotational and repositioning movements, staged IPR for room, and a retainer afterward to hold the corrected bite in place.
Left uncorrected, an anterior crossbite can wear down the edges of the affected teeth over time and put uneven stress on the bite — another reason it's worth addressing rather than leaving alone. See our Understanding Your Bite guide for more on crossbites and other bite types.
Retainers: Not Just for After Orthodontic Treatment
Teeth have a natural tendency to drift over time — a retainer isn't only for holding a smile in place right after Invisalign or braces.
Vivera® Retainers
Made from the same durable, medical-grade material as Invisalign aligners, Vivera retainers are custom-fitted to hold your teeth in their current position. We recommend them after orthodontic treatment, but they're also a good option any time you want to protect your current alignment from natural drift — teeth continue to shift gradually throughout life, even without prior orthodontic work.
Vivera retainers can also be made with anterior stoppers for patients who clench their teeth, creating a small gap between the back teeth that helps reduce or eliminate the ability to clench down with full force.
Hawley Retainers
For patients who want a more durable, long-lasting option, we also offer Hawley retainers — a classic wire-and-acrylic design that can be adjusted over time and tends to hold up longer than clear plastic retainers with everyday wear.
Bonded (Fixed) Lingual Retainers
A bonded retainer is a thin wire cemented to the back of the lower (and sometimes upper) front teeth, holding them in place without any daily effort on your part. It's the most effective option for keeping lower front teeth stable long-term precisely because it doesn't depend on remembering to wear anything — a real advantage for a tooth alignment that has a lifelong tendency to relapse.
The trade-off is that a bonded wire needs more hygiene attention around it (it can trap plaque if flossing underneath is skipped), and if it distorts or partially debonds without your noticing, it can occasionally push a tooth out of position rather than holding it — something we check for at your regular visits.
Combining Fixed and Removable Retention
For cases with a higher relapse risk — significant crowding, expansion, or a large bite correction — we sometimes recommend a bonded wire plus a removable retainer worn on top at night. The two together provide more stability than either alone, particularly in the lower arch.
Removing or Replacing a Bonded Retainer
A bonded retainer isn't meant to come off and simply not be replaced — here's what to know if yours needs to be removed.
Why Removal Isn't the End of the Story
Lower front teeth are the most relapse-prone in the mouth: without some form of ongoing retention, irregularity can return in the majority of cases within a couple of years, and the natural tendency for teeth to drift continues for life regardless of whether you had braces or Invisalign. Removing a bonded retainer without planning a replacement — a new bonded wire or a removable retainer — leaves that alignment unprotected.
There's also a less obvious issue: a bonded wire that has quietly gone out of shape or partially debonded before removal can leave affected teeth already out of position, sometimes with mild gum recession where a tooth has been pushed outward. In more pronounced cases, this can call for orthodontic (and occasionally periodontal) evaluation rather than a simple removal — another reason we check the wire and the teeth around it before taking it off, not just after.
What Happens at Removal
Removing a bonded retainer means debonding it from the enamel and cleaning off the leftover cement, which we do carefully to avoid scratching or over-polishing the tooth surface underneath. If there's been plaque or mild gum inflammation building up around the wire — common with fixed retainers over time — we'll address that at the same visit.
Option 1: A New Bonded Retainer
Still the most effective way to hold the lower arch stable long-term, since it doesn't rely on remembering to wear anything. A rectangular (braided) wire tends to outperform a round wire for stability, though it does mean somewhat more plaque control around it.
Option 2: A Removable Retainer
A clear (Vivera-type) or Hawley retainer is easier to keep clean and depends on consistent wear, typically nightly for the long term. In the upper arch it holds up just as well as a bonded wire; in the lower arch it allows a bit more movement over time, usually modest.
Option 3: Both Together
A new bonded wire plus a removable retainer worn over it gives the most stability of the three options, particularly for cases that had significant crowding, expansion, or a large bite correction — the removable layer adds backup resistance the bonded wire alone doesn't provide.
Whichever direction makes sense for your case, the short version is the same: don't leave a lower arch unretained after a bonded wire comes off. We'll walk through which replacement option fits your specific alignment history and habits at your visit.
“Am I a Candidate for Invisalign?” Quiz
Answer all 5 questions, then click “See My Result” below.
This quiz is an educational screening tool, not a diagnosis. A consultation with digital scans confirms candidacy for Invisalign®.
Care From a Team That Knows You
Dr. Boris Zusin is an expert in general, cosmetic, implant, and dental sleep medicine, with 30+ years of clinical experience and ongoing continuing education. Lena Zusin, RDH works alongside him to make every visit as warm and comfortable as possible.
“Drawing upon our combined skills refined through years of experience and continued education, Lena and I will do everything possible to ensure that your entire dental experience at our office is as good as possible.” — Dr. Boris Zusin
- Uncompromising clinical excellence
- Meticulous attention to detail
- A gentle approach to dentistry

FAQ: Invisalign® at Zusin Dental, NYC
Invisalign uses a series of custom-made, clear, nearly invisible aligners — sometimes called clear braces — that gradually move your teeth into the desired position. Each aligner is typically worn for about a week before switching to the next one in the series. We use digital scans and 3D imaging to plan your treatment and predict results.
Most people see the results they want in 12–18 months; minor corrections can finish in about 6 months, more involved cases may take 24+ months. Aligners need to be worn 20–22 hours a day, removed only for eating, drinking, brushing, and flossing.
Yes — Dr. Boris Zusin is a recognized Invisalign® Preferred Provider. He has offered Invisalign since 2000 and completed hundreds of cases since then, as part of 30+ years practicing dentistry (he opened his practice in 1995).
Invisalign's clear, removable aligners are great for a discreet treatment with no dietary restrictions, but results depend on wearing them 20–22 hours a day. Traditional braces can handle more complex tooth movements since they're fixed and don't depend on patient compliance.
Many plans (Delta Dental, Aetna, Cigna, and others) cover Invisalign similarly to traditional braces, often as a percentage of cost or a lifetime orthodontic maximum (commonly $1,000–$3,000). We'll check your coverage and give you a clear out-of-pocket estimate.
Yes — Invisalign can correct overbite, underbite, crossbite, open bite, crowding, spacing, and can move molars into proper alignment for mild to moderate cases. More complex corrections may need attachments or a more individualized approach.
It's worth correcting sooner rather than later: a severe, longstanding overbite can put the lower front teeth under constant abnormal pressure from the upper teeth, wearing them down and, in advanced cases, contributing to tooth loss like the example below. Addressing a significant bite misalignment isn't just cosmetic — it protects the teeth that are bearing the brunt of it.
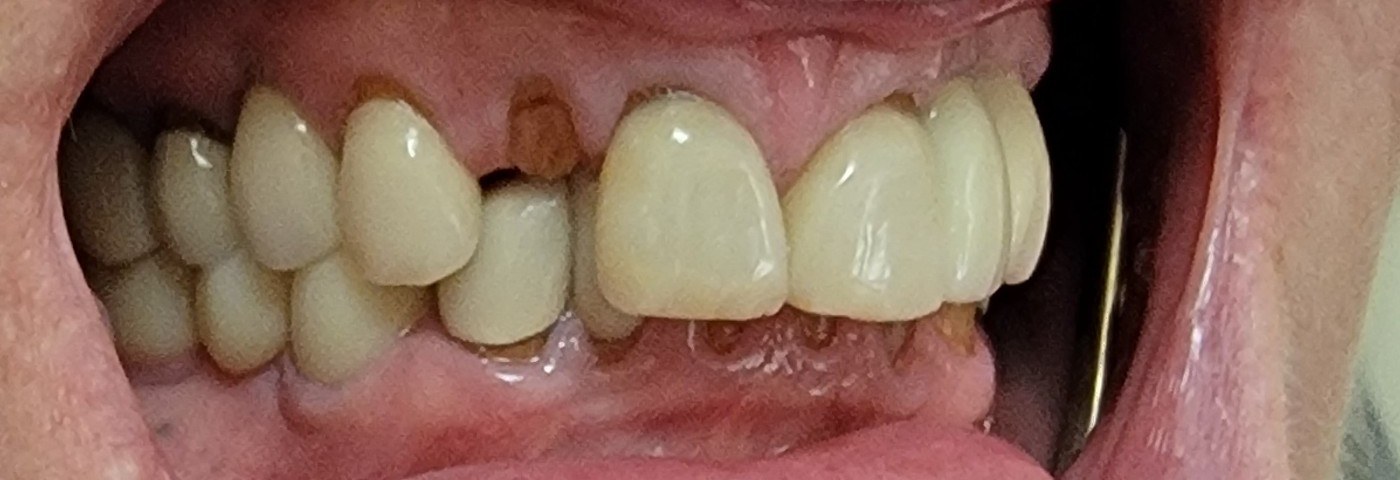
Yes — for younger patients in particular, Invisalign can gently widen a narrow dental arch, creating more room for teeth to come in properly. Expanding the arch can also open up more space for the tongue and airway, which in many cases helps with nasal breathing. This is often best addressed early, as part of a growth-focused evaluation.
Remove your aligners before eating; water is fine to drink while wearing them, but other beverages (especially hot drinks like coffee and tea) can stain, crack, or warp the plastic.
Clean them twice a day with a soft toothbrush and lukewarm water — avoid hot water (can warp the plastic) and toothpaste (can scratch and cloud the surface). Invisalign Cleaning Crystals or a gentle antibacterial soap also work well.
Attachments are small tooth-colored bumps that guide tooth movement; buttons are used with elastics for bite correction; chewies are soft aids you bite on to help seat the aligner fully. We map out placement and supply what you need.
Mild pressure when starting a new set of aligners is normal and usually resolves within 24–72 hours — it's a sign the aligners are working. Switching aligners at night and using a bit of wax on rough edges can help. See our full guide to Invisalign pain for exactly how much to expect and what helps most.
Most cases need around 20–40 trays; minor fixes may need only 10–15. More complex movement may require additional refinement trays, which is common and usually included in the treatment plan.
A full comprehensive treatment typically runs about $3,500–$8,000 in New York City. Insurance often covers 25–50% depending on your orthodontic benefits, and we offer financing/payment plans.
Faint white patches where a bracket or aligner tray sat are a common finding after orthodontic treatment — they're the result of plaque demineralizing the enamel underneath during treatment. If this happens, Icon resin infiltration can treat it in a single visit, without drilling or anesthesia.
Call 212-877-7475 or text 917-693-8269 to book your first appointment, or schedule online. At your visit, Dr. Boris Zusin and his team will give you a thorough exam, formulate a custom plan, and verify your insurance coverage.
Adult teeth can move at any age — there's no upper age limit for Invisalign as long as your teeth and gums are healthy enough to support tooth movement. In fact, adults now make up a large share of Invisalign patients overall, often correcting shifting or crowding that developed years after braces (or that was never treated in the first place). Gum disease, if present, needs to be brought under control first, since moving teeth through unhealthy bone isn't advisable.
Yes — beyond whatever your insurance covers, we offer in-house and third-party financing options to spread the remaining cost over monthly payments rather than paying it all upfront. We'll walk through the specific numbers for your treatment plan, insurance benefit, and preferred payment structure at your consultation. See our full Invisalign cost breakdown for typical pricing.
Your first visit covers a full oral exam to confirm your teeth and gums are healthy enough for treatment, a digital 3D scan of your bite (no goopy impression trays), and a walkthrough of your projected treatment plan — including a rough preview of your final result, estimated timeline, and cost. If everything looks good, your custom aligners are ordered from there.
Call us right away rather than skipping ahead to the next tray in the series or going without one for an extended stretch, either of which can shift your progress off track. Depending on how far along you are, we may have you move to the next aligner early, temporarily wear a previous one, or order a replacement — we'll tell you which makes sense for your specific case.
Yes — teeth naturally drift over time, and a retainer is what holds your result in place after active treatment ends. Most patients wear a retainer nightly for the long term after an initial full-time period. See our guide on caring for a retainer for how to keep it in good shape.
Invisalign Teen is specifically designed for younger patients still growing into their permanent teeth, with features like compliance indicators and replacement aligners built into the plan for a lost or damaged tray. See our full Invisalign Teen guide for parents.
Yes. Lower front teeth are the most relapse-prone in the mouth, and that tendency doesn't go away just because a bonded wire comes off — without a replacement, misalignment often returns within a couple of years. We'll always plan a next step at the same visit, whether that's a new bonded wire, a removable retainer, or both together for higher-relapse cases. See below for how we approach retainers long-term.
Real Solutions For Real Patients
A real Zusin Dental Invisalign case: crowding resolved and arch form improved, before and after.
A second real Zusin Dental Invisalign case: crowding resolved, before and after.
A third real Zusin Dental Invisalign case: crowding and an anterior crossbite resolved, before and after.
Sources
- Clear Aligners in Orthodontic Treatment — Weir T, Australian Dental Journal (2017)
- Computer-Aided Design/Computer-Aided Manufacturing Technology in Customized Orthodontic Appliances — Grauer D, Wiechmann D, Heymann GC, Swift EJ, Journal of Esthetic and Restorative Dentistry (2012)
- Enhancing the Predictability of Tooth Movements With Clear Aligners — Part 1: Biomechanical Considerations and Determinant Factors — Long H, Park JH, American Journal of Orthodontics and Dentofacial Orthopedics (2026)
- The Effectiveness of Aligners in the Treatment of Anterior Open Bite in Adult Patients: A Systematic Review and Critical Appraisal — MDPI (2024)
- The Efficacy of Anterior Open Bite Closure When Using Invisalign's Optimized Extrusion Versus Conventional Attachments — Journal of the World Federation of Orthodontists (2023)
- Is Maxillary Arch Expansion With Invisalign Efficient and Predictable? A Systematic Review — International Orthodontics (2023)
- Quality and Stability of Orthodontic Treatment Outcomes With Clear Aligners Versus Fixed Appliances: A Systematic Review and Meta-Analysis — Alhafi ZM, Hajeer MY, Alam MK, Jaber ST, European Journal of Orthodontics (2025)
- Treatment Outcome With Orthodontic Aligners and Fixed Appliances: A Systematic Review With Meta-Analyses — Papageorgiou SN, Koletsi D, Iliadi A, Peltomaki T, Eliades T, European Journal of Orthodontics (2020)
- Clinical Effectiveness of Clear Aligner Treatment Compared to Fixed Appliance Treatment: An Overview of Systematic Reviews — Yassir YA, Nabbat SA, McIntyre GT, Bearn DR, Clinical Oral Investigations (2022)
- Comparison of Maxillary Anterior Tooth Movement Between Invisalign and Fixed Appliances — Murphy SJ, Lee S, Scharm JC, et al., American Journal of Orthodontics and Dentofacial Orthopedics (2023)
- What Percentage of Patients Switch From Invisalign to Braces? A Retrospective Study Evaluating the Conversion Rate, Number of Refinement Scans, and Length of Treatment — Kravitz ND, Dalloul B, Zaid YA, Shah C, Vaid NR, American Journal of Orthodontics and Dentofacial Orthopedics (2023)
- Retention and Relapse in Clinical Practice — Littlewood SJ, Kandasamy S, Huang G, Australian Dental Journal (2017)
- Retention Procedures for Stabilising Tooth Position After Treatment With Orthodontic Braces — Martin C, Littlewood SJ, Millett DT, et al., Cochrane Database of Systematic Reviews (2023)
- The Dark Side of Fixed Retainers: Case Series — Abu Arqub S, Al-Moghrabi D, Tsichlaki A, Sanders D, Uribe F, American Journal of Orthodontics and Dentofacial Orthopedics (2023)
- Inadvertent Tooth Movement With Fixed Lingual Retainers — Shaughnessy TG, Proffit WR, Samara SA, American Journal of Orthodontics and Dentofacial Orthopedics (2016)
- Comparison of Efficacy of Thermoplastic Retainer With Round and Rectangular Bonded Lingual Wire Retainer in the Mandible Two Years After Orthodontic Treatment: A Randomised Controlled Trial — Kanizaj Ugrin S, Špalj S, Clinical Oral Investigations (2024)
- Effects of Fixed Orthodontic Lingual Retainers on PDL Stress, Root Resorption Risk, and Tooth Displacement — Moradinejad M, Mazhari M, Mazhary M, et al., Scientific Reports (2025)
- Post-Treatment Stability After Insertion of CAD/CAM Fabricated or Conventional Fixed Orthodontic Retainers: A Two-Year Follow-Up — Tabellion M, Simgen J, Lisson JA, Clinical Oral Investigations (2025)
- Gingival Health and Relapse Tendency: A Split Mouth Randomized Controlled Trial of Two Positions of Lower Fixed Retainers — Al-Nimri K, Al-Qaqaa S, Clinical Oral Investigations (2024)
- The Effects of Fixed Orthodontic Retainers on Periodontal Health: A Systematic Review — Arn ML, Dritsas K, Pandis N, Kloukos D, American Journal of Orthodontics and Dentofacial Orthopedics (2020)
- Complications and Treatment Errors Involving Periodontal Tissues Related to Orthodontic Therapy — Jepsen K, Sculean A, Jepsen S, Periodontology 2000 (2023)
- A Randomised Controlled Trial Comparing Thermoformed and 3D-Printed Retainers in Young Adults: Evaluation of Post-Treatment Stability and Patient Satisfaction — Boo HS, Mohd Tahir NNZ, Bahar AD, Littlewood SJ, Sivarajan S, Clinical Oral Investigations (2026)
- Treatment Stability With Bonded Versus Vacuum-Formed Retainers: A Systematic Review of Randomized Clinical Trials — Bellini-Pereira SA, Aliaga-Del Castillo A, Dos Santos CCO, et al., European Journal of Orthodontics (2022)
- Bonded Versus Vacuum-Formed Retainers: A Randomized Controlled Trial. Part 1: Stability, Retainer Survival, and Patient Satisfaction Outcomes After 12 Months — Forde K, Storey M, Littlewood SJ, et al., European Journal of Orthodontics (2018)
- Effectiveness of Bonded and Vacuum-Formed Retainers: A Prospective Randomized Controlled Clinical Trial — O'Rourke N, Albeedh H, Sharma P, Johal A, American Journal of Orthodontics and Dentofacial Orthopedics (2016)
- Post-Treatment Stability in Orthodontic Retention With Twistflex Retainers — Do Patients Benefit From Additional Removable Retainers? — Knaup I, Schulte U, Bartz JR, et al., Clinical Oral Investigations (2022)
- Three-Dimensional Stability During Orthodontic Retention: A Comparative Analysis of Conventional, CAD/CAM-Fabricated, and Robotically Bent Fixed Retainers Versus Removable Appliances — Köck J, Lang F, Niederau C, et al., Clinical Oral Investigations (2026)
- A Randomized Controlled Trial Comparing Retainers in Bimaxillary Proclination Cases — Maskim N, Mohd Tahir NNZ, Wan Hassan WN, Clinical Oral Investigations (2025)
- Post-Treatment Stability After 5 Years of Retention With Vacuum-Formed and Bonded Retainers — A Randomized Controlled Trial — Krämer A, Sjöström M, Apelthun C, Hallman M, Feldmann I, European Journal of Orthodontics (2023)
Your Experience Matters To Us
5.0 out of 5 on Google (54 reviews) · 4.99 out of 5 on Zocdoc (227 reviews)
“Knowledge is an understatement when you talk about Dr. Zusin! My family and I have been patients of his for over 20 years. I always feel I am given the best advice and never pressured into any unnecessary treatment.”
Faina S. · View on Google →
“I tried a couple different dentists in NYC and Zusin Dental is the best. They are thorough, they don't try and upsell you services you don't need, and they offer appointments on Saturday. The best cleaning I ever had!”
Gordon T. · View on Google →
“Routinely SUPERB level of care, including Dr. Zusin having made himself available for emergent care when needed. The office is always spotlessly clean and there is no waiting at appointment time. Pain-free dentistry!”
Anil N. · View on Google →
“I have never experienced pain with Dr. Zusin. For a practice in busy Manhattan, their office has a small town feel, very relaxed and personable. Lena is always quick to respond to appointment requests or changes.”
Molly P. · View on Google →
“Dr. Zusin is the best dentist! I have been visiting his office for the majority of my life. He has expertly performed teeth whitening and Invisalign, and continued to save my teeth after I chipped my two front teeth.”
Sasha S. · View on Google →
“The West End office is state of the art and very relaxing. Dr. Zusin and Lena are a great team. No matter the dental problem you will get the best results. I highly recommend them.”
Domingo Q. · View on Google →
Ready to Get Started?
You will never be treated like a statistic at Zusin Dental. Let's talk about what's right for you.
Schedule Your Visit Call 212-877-7475